
Graphical Abstract
Introduction
Invasive fungal infections (IFIs) remain a major cause of morbidity and mortality among immunocompromised patients, particularly those with hematologic malignancies, recipients of hematopoietic stem cell transplantation (HSCT), and individuals exposed to prolonged or profound immunosuppression. Despite advances in diagnostic tools and antifungal therapeutics, outcomes of IFIs, especially invasive aspergillosis and infections caused by other filamentous fungi, remain poor, with reported mortality rates frequently exceeding 30–50% in high‑risk populations (1–3). The evolving epidemiology of fungal infections, characterized by increasing mold diversity, emerging antifungal resistance, and a growing population of at‑risk patients, has further complicated prevention and management strategies (4,5).
Among available systemic antifungal agents, triazoles constitute the backbone of both prophylaxis and treatment of mold infections. Posaconazole, an extended‑spectrum triazole structurally related to itraconazole, has emerged as a key antifungal agent owing to its broad spectrum of activity, including Aspergillus spp., many Mucorales, and a wide range of rare molds (6,7). Since its initial clinical introduction, posaconazole has evolved substantially, with improved formulations including delayed‑release tablets and an intravenous (IV) preparation that largely overcome the pharmacokinetic limitations of the original oral suspension (8,9). These advances have significantly broadened its clinical applicability across diverse patient populations and care settings.
Randomized controlled trials have firmly established posaconazole as a preferred agent for primary antifungal prophylaxis in patients with acute myeloid leukemia (AML), myelodysplastic syndromes (MDS), and allogeneic HSCT recipients with graft‑versus‑host disease (GVHD), demonstrating superior efficacy compared with fluconazole or itraconazole in preventing IFIs and reducing infection‑related mortality (10–12). Consequently, posaconazole is strongly recommended in major international guidelines, including those of the European Conference on Infections in Leukemia (ECIL), the Infectious Diseases Society of America (IDSA), and other organizations (13–15).
Beyond prophylaxis, posaconazole also plays an important role in the treatment of IFIs, particularly as salvage therapy or as an alternative for patients intolerant of or refractory to first‑line agents such as voriconazole or liposomal amphotericin B (L-AmB) (16,17). Its favorable tolerability profile, lower incidence of neurological adverse effects compared with voriconazole, and availability in both oral and IV formulations support its use in prolonged treatment courses and in clinically complex patients (18,19). Nevertheless, the optimal positioning of posaconazole in treatment algorithms requires careful consideration of multiple factors, including prior antifungal exposure, pharmacokinetic variability, drug-drug interactions, and local epidemiology and resistance patterns.
The clinical landscape in which posaconazole is used has also changed substantially over the past decade. Novel anticancer therapies such as targeted kinase inhibitors, B-cell lymphoma 2 (BCL‑2) inhibitors, immune checkpoint inhibitors, chimeric antigen receptor (CAR) T‑cell therapies, and bispecific antibodies have transformed outcomes in both hematologic and solid malignancies. However, these advances have also introduced new patterns of immune dysfunction and susceptibility to fungal infections (20–22). In parallel, virus‑associated fungal infections, particularly influenza‑associated and coronavirus disease 2019 (COVID‑19)-associated pulmonary aspergillosis, have emerged as major clinical challenges, extending the relevance of mold‑active antifungal agents beyond traditionally immunocompromised populations (23–25).
Despite extensive clinical experience, posaconazole use in routine practice is frequently complicated by formulation‑dependent pharmacokinetics, clinically significant drug-drug interactions, and ongoing uncertainty about the role of therapeutic drug monitoring (TDM) in different clinical scenarios (26–28). Furthermore, evidence gaps persist regarding its optimal use in special populations and the management of breakthrough infections (29,30). Collectively, these complexities underscore the need for an updated, clinically focused synthesis of current evidence and expert experience regarding posaconazole across the spectrum of IFI prophylaxis and treatment.
This narrative review was developed by a multidisciplinary panel of clinicians with expertise in infectious diseases, clinical mycology, and hematology. The panel reviewed the current literature on posaconazole, including randomized controlled trials, observational studies, meta‑analyses, pharmacokinetic and pharmacodynamic investigations, and international clinical guidelines. Evidence was identified through targeted searches of PubMed/MEDLINE and major guideline repositories, focusing on publications in English between January 1, 2000, and March 30, 2026. Current guidelines were obtained from the websites of the European Conference on Infections in Leukemia (ECIL), the European Society of Clinical Microbiology and Infectious Diseases (ESCMID), the European Confederation of Medical Mycology (ECMM), the Infectious Diseases Society of America (IDSA), the European Organization for Research and Treatment of Cancer/Mycoses Study Group Education and Research Consortium (EORTC/MSGERC) and the National Comprehensive Cancer Network (NCCN). Reference lists of key reviews and guidelines were also hand-searched to identify additional relevant studies. Consensus recommendations were achieved through several online discussions and reflect collective clinical judgment rather than formal grading of evidence. The resulting statements aim to provide practical, clinically applicable guidance while addressing existing evidence gaps and areas requiring further investigation.
Chemical Structure and Unique Features
Azoles are aromatic, five-membered heterocyclic compounds that contain at least one nitrogen atom and two double bonds within the ring structure. The ring may also incorporate oxygen or sulfur atoms, leading to distinct parent heterocycles. Among these, imidazoles and triazoles constitute the two major classes of azole antifungal agents used in clinical practice (31).
Triazole antifungal agents are known to possess distinct pharmacokinetic profiles. Posaconazole is an extended-spectrum triazole that is structurally similar to the older broad-spectrum agent itraconazole. However, it differs by featuring fluorine substituents instead of chlorine and a furan ring instead of the dioxolane ring. It contains a long, hydroxylated side chain that facilitates multiple binding interactions with lanosterol 14-α-demethylase (CYP51), leading to increased binding stability even in the presence of mutated enzymes. This structural flexibility underpins its activity against azole-resistant Aspergillus spp. and Mucorales, a key distinction from voriconazole or fluconazole (32).
Understanding how individual agents differ in their metabolic pathways and routes of elimination is essential for safe, effective use, particularly in medically complex patients vulnerable to fungal infections. Posaconazole illustrates this variability well, as its pharmacokinetic profile differs substantially from other triazoles and varies significantly between its oral suspension, delayed-release tablet, and IV formulations.
The preferred formulations of posaconazole are the IV form and delayed-release tablets. The IV formulation, approved for use in patients aged 2 years and older, is particularly valuable when oral therapy is not feasible or when impaired gastrointestinal absorption is a concern. The delayed-release tablets approved for the same age group (patients 2 years of age and older) constitute the preferred oral formulation. In a study involving neutropenic patients at high risk for IFIs, participants received either 200 mg or 300 mg of posaconazole delayed-release tablets once daily, following a twice-daily loading dose on day 1 in both groups, with no restrictions related to food intake. By day 8, target pharmacokinetic exposure was achieved in 15 of 19 patients (79%) in the 200 mg group and in 31 of 32 patients (97%) in the 300 mg group (33). Additional studies have consistently demonstrated that delayed-release tablets result in higher serum posaconazole concentrations than the oral suspension, particularly when administered under fasting conditions (34,35).
While posaconazole is available as both immediate-release and delayed-release oral suspension formulations, these are not preferred due to significant pharmacokinetic variability. The immediate-release oral suspension is approved for use in patients aged 2 years and older, whereas the delayed-release oral suspension is approved only for pediatric patients 2 years of age and older who weigh 40 kg or less. Adequate absorption of the oral suspension depends on concomitant oral intake and is optimized when administered with a high-fat meal or nutritional supplement (36). Gastrointestinal dysfunction such as GVHD or mucositis can significantly reduce posaconazole absorption (37). Additionally, absorption of the oral suspension appears to plateau at a total daily dose of approximately 800 mg and is enhanced when the total dose is divided into multiple daily administrations. Studies have demonstrated that administering the same total daily dose in four divided doses, rather than two, results in higher total serum concentrations (36). In clinical practice, delayed-release tablets or IV therapy are generally preferred over the oral suspension for patients with mucositis, GVHD, diarrhea, or poor oral intake to minimize the risk of subtherapeutic exposure (9).
Approximately 15% of a posaconazole dose undergoes hepatic metabolism via non-cytochrome P450 (CYP) pathways to inactive metabolites, which are eliminated in both urine and feces. The primary route of elimination is fecal excretion of the unchanged parent compound, accounting for roughly 77% of total clearance. Because posaconazole is eliminated predominantly in feces, with minimal urinary recovery, it should not be relied upon to treat urinary tract infections, and dose adjustment is generally unnecessary in renal impairment (38).
Posaconazole is a potent inhibitor of CYP3A4 and the P-glycoprotein (P-gp) efflux transporter, creating potential for clinically significant drug interactions. Coadministration with CYP3A4 or P-gp substrates, including calcineurin inhibitors, mTOR inhibitors, certain chemotherapeutic agents, and selected cardiovascular drugs may increase systemic exposure to these medications, warranting careful TDM and dose adjustment (36,38).
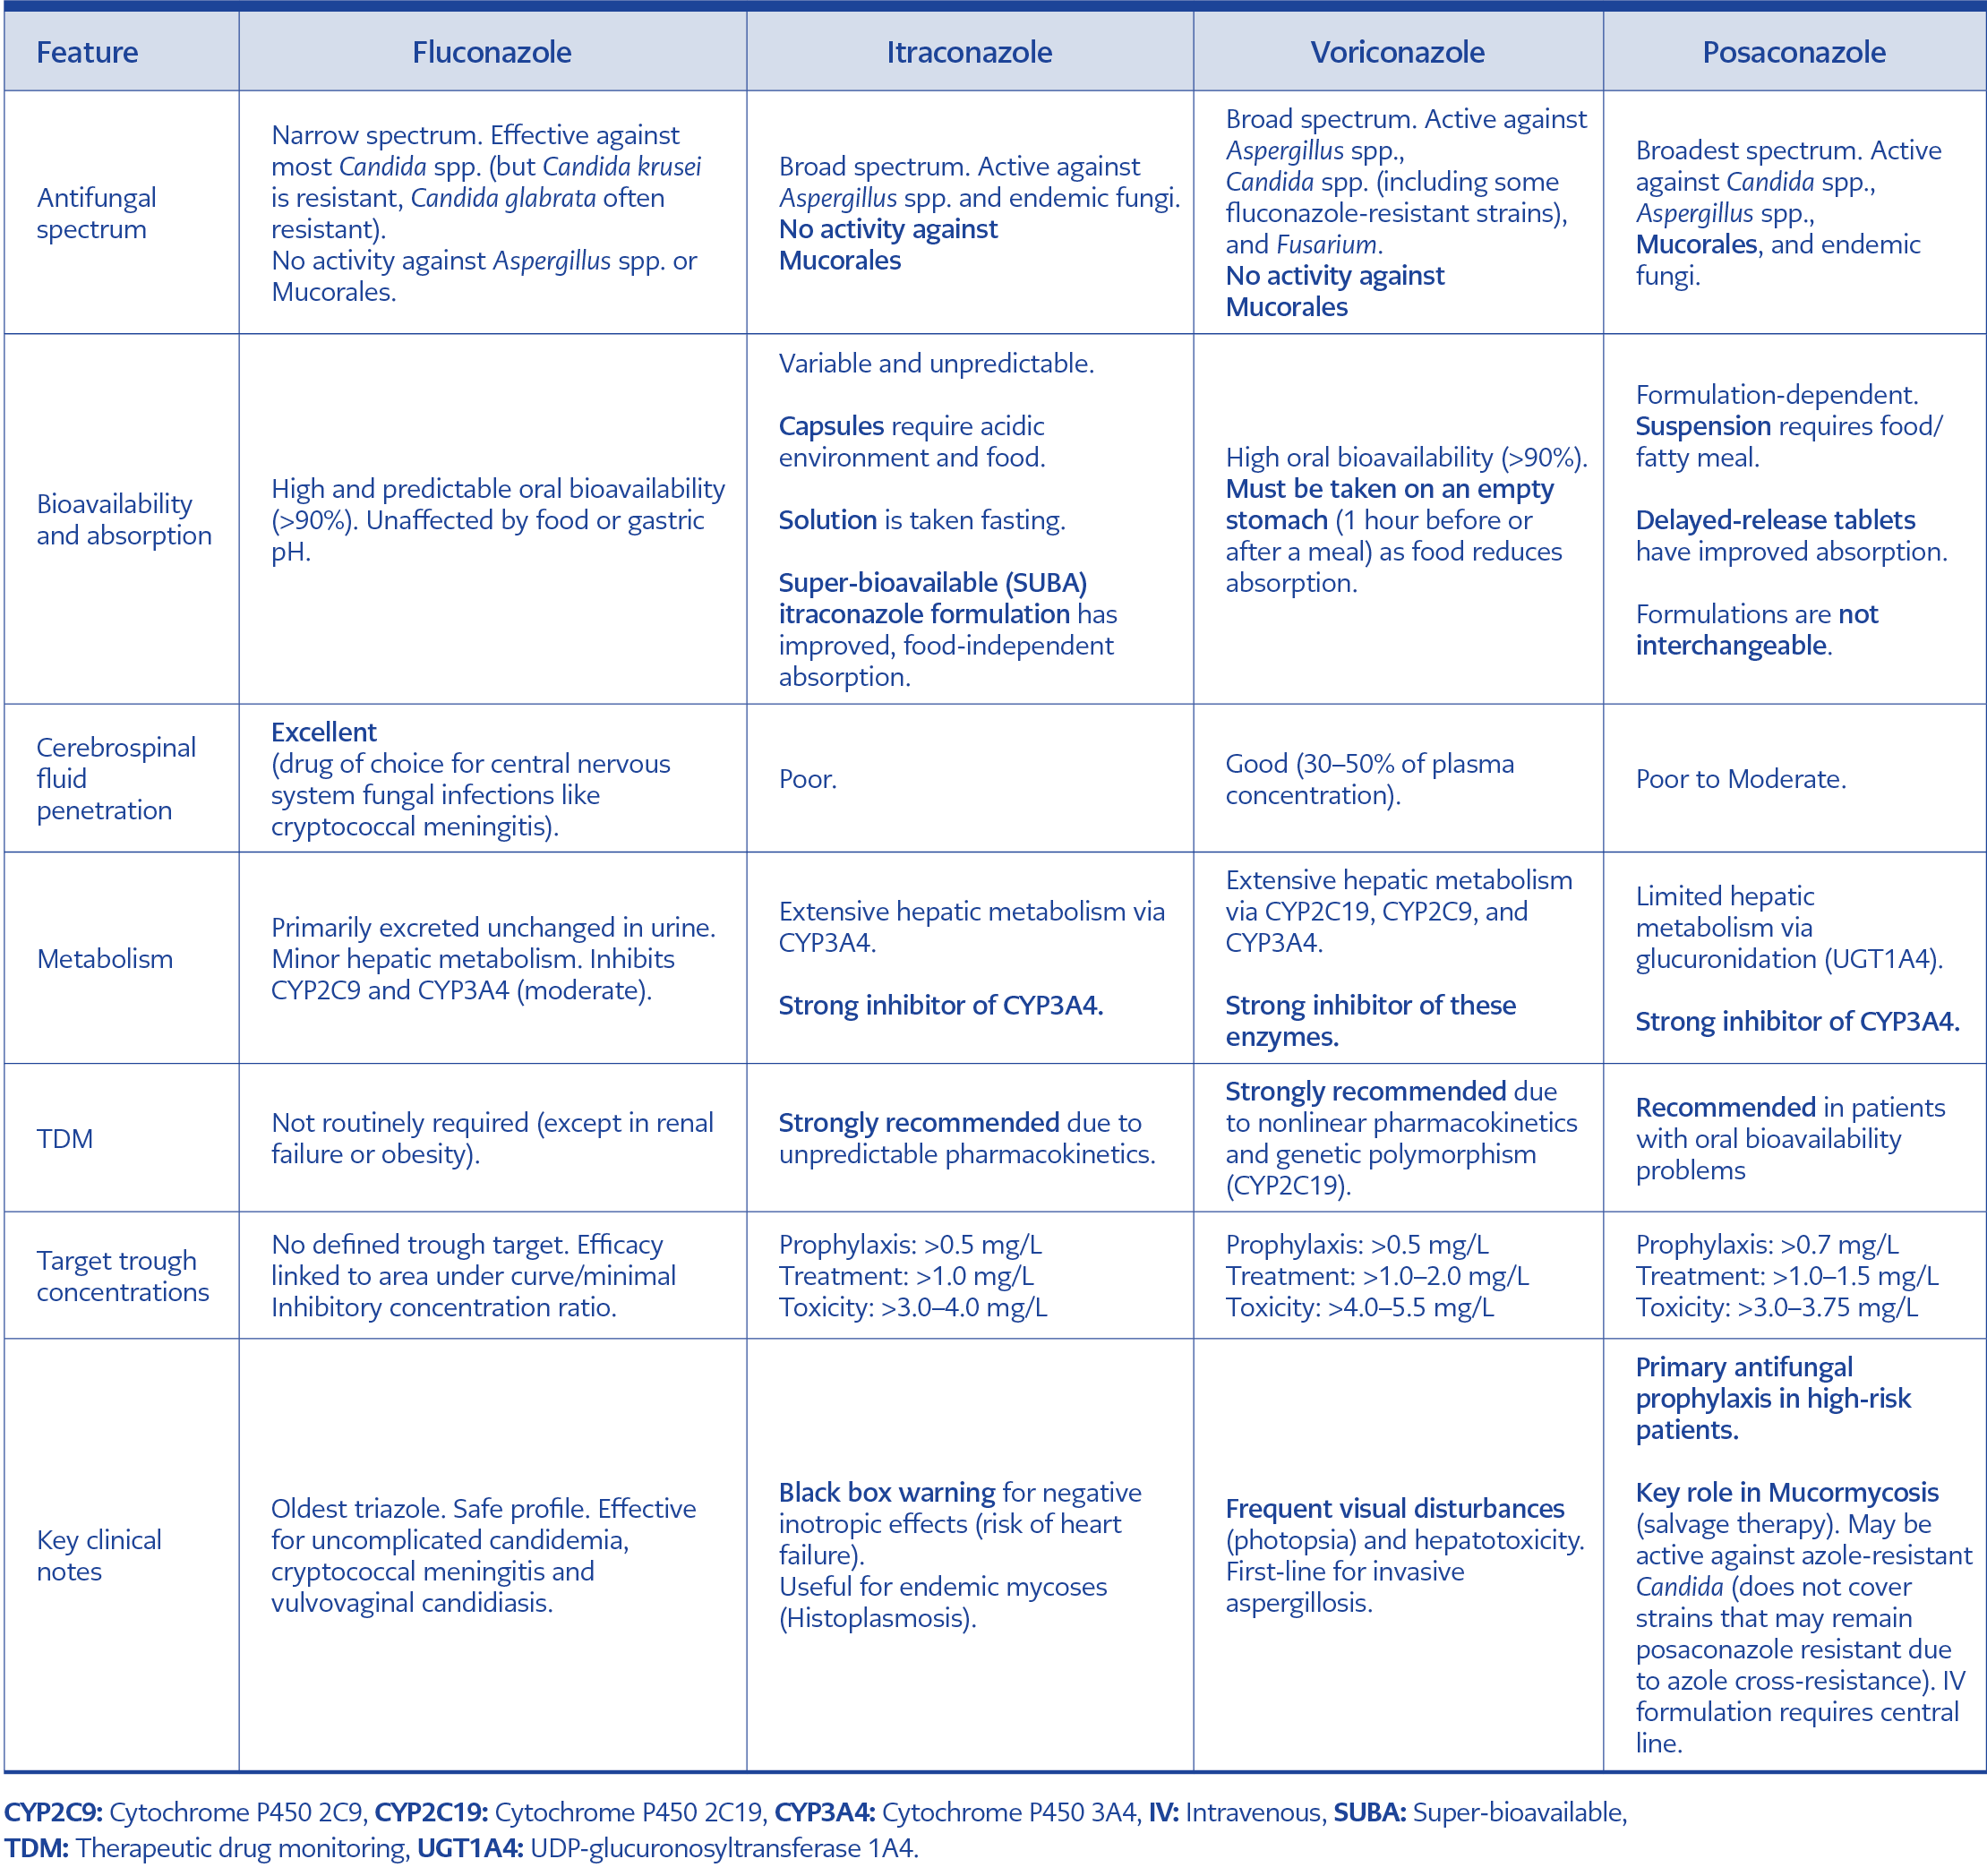
Table 1. General comparison of triazole antifungals available in Türkiye (39–41).
Posaconazole distinguishes itself from other triazole antifungals through its broader mold coverage and greater pharmacokinetic complexity, securing its essential role in the prophylaxis and treatment of high-risk patient populations. Table 1 highlights key distinctions between posaconazole and other triazoles, particularly regarding mold activity, pharmacokinetic variability, and clinically relevant drug-drug interactions. The effective clinical use of posaconazole requires informed formulation selection, management of significant drug interactions, and monitoring of systemic exposure.
Pharmacokinetics and Pharmacodynamics of Posaconazole
Absorption, Distribution, Metabolism, and Elimination
Absorption of posaconazole is highly variable, particularly for the oral suspension, which has saturable bioavailability (F) that is drastically reduced by factors such as increased gastric pH, diarrhea, and mucositis. In contrast, absorption from the delayed-release tablet is more consistent and less affected by gastric conditions (9).
Distribution is extensive, with a large volume of distribution (VD) and high tissue accumulation, especially in the lungs, but penetration into the central nervous system and eye is low and inconsistent (42–44). The drug is over 98% protein-bound (9). The VD differs significantly among formulations. Oral suspension has the largest VD at 1774 L, indicating extensive tissue distribution. The delayed-release tablet has a moderate VD of 394 L, while the IV solution has the smallest VD at 261 L (45).
Unlike other azoles, posaconazole undergoes minimal metabolism by the CYP system. It is primarily metabolized via uridine diphosphate-glucuronosyltransferase (UGT), specifically UGT1A4, with about 17% of the dose being glucuronidated. Most of the drug (77%) is excreted unchanged in the feces, with renal elimination accounting for only 13% of the dose, of which <0.2% is unchanged (46). Intestinal bile salts play a critical role in the absorption of posaconazole (47). The apparent clearance (CL/F) of the oral suspension is highly variable and increases under conditions that reduce bioavailability, whereas the clearance of the delayed-release tablet and IV formulations is more stable. Its elimination half-life is long (approximately 24–35 hours), allowing once-daily dosing with the tablet and IV formulations after an initial loading dose. Posaconazole is a potent CYP3A4 inhibitor and a target of UGT inducers, leading to complex drug-drug interactions (9).
Formulation-Dependent Differences in Bioavailability
The pharmacokinetics of posaconazole are largely determined by the formulation used. Oral suspension exhibits saturable, erratic, and highly variable absorption. Its bioavailability is profoundly influenced by gastric conditions. A high-fat meal can increase exposure (area under the curve [AUC]) by up to 400%, while fasting conditions result in very low levels. Its absorption is dose-limited above a total daily dose of 800 mg (9). The delayed-release tablet bypasses the erratic gastric environment by releasing posaconazole in the small intestine. It shows linear pharmacokinetics and significantly higher and more consistent bioavailability. Food has a modest impact (~50% increase in AUC), and it is less affected by factors that alter gastric pH or motility (45). Consistent evidence from clinical studies demonstrates the superior bioavailability of the delayed-release tablet formulation of posaconazole compared with the oral suspension. Across multiple studies, target serum concentration attainment rates are significantly higher with the tablet (91%, 62.5%, and 81.3%) than with the suspension (37%, 51.6%, and 51%) (35,48,49). A retrospective analysis from Hacettepe University Hospital found a median serum concentration of 1.45 mg/L for the delayed-release tablet with 74.3% of measurements exceeding the target threshold of 0.7 mg/L (50).
Differences Among Posaconazole Formulations
Oral suspension has the most complex dosing, requiring multiple daily doses (200 mg/3–4 times daily) with food to ensure adequate absorption. It is the only formulation indicated for oropharyngeal candidiasis. Delayed-release tablet and IV solutions share a simpler dosing regimen: a loading dose twice on day one (600 mg), followed by once-daily maintenance (300 mg). The time to maximum serum concentration (Tmax) is fastest for the IV solution, occurring at 90 minutes at the end of the infusion. The oral suspension reaches Tmax at 3 hours, and the delayed-release tablet has the slowest absorption, with a Tmax of 4 to 5 hours. The half-life (t1/2) is relatively consistent across formulations. The oral suspension has the longest mean half-life at 35 hours (range 20–66 h), followed by the delayed-release tablet at 29 hours (range 26–31 h), and the IV solution at 27 hours. The time to reach steady state is longer for oral suspension (7–10 days) than for both the delayed-release tablet and the IV solution, which each reach steady state in 6 days (9,45).
Factors Affecting Serum Posaconazole Levels
Gastrointestinal factors substantially influence posaconazole exposure. Diarrhea substantially reduces concentrations of both oral suspension and delayed-release tablet (51,52). Impact of vomiting on posaconazole concentrations was not identified (53). Diet can influence posaconazole serum concentrations. A study in healthy volunteers (54) reported that taking a single 400 mg dose with a nutritional supplement caused a 3.4-fold increase in the maximum serum concentration. There was a food effect on the reference product of posaconazole but not on the bioequivalent product of posaconazole (55).
Drug-drug interactions are critical. Concomitant use of enzyme inducers such as rifabutin and phenytoin significantly reduces posaconazole levels (56,57). Furthermore, acid-suppressing therapy notably decreases concentrations of oral suspension but has no significant effect on delayed-release tablet (58,59). Co-administration of the gastric stimulant metoclopramide decreased posaconazole concentrations in pediatric patients (60).
Several factors, including age, sex, and renal or hepatic impairment, did not significantly influence posaconazole concentrations (53). However, genetic polymorphisms specifically the UGT1A4*3 genotype, are associated with lower posaconazole concentrations (61). Obesity was reported as a risk factor for subtherapeutic posaconazole concentrations (62). Patients with a body weight ≥90 kg or a body mass index (BMI) ≥30 had significantly lower mean trough levels compared to their counterparts.
Based on the meta-analysis of 10 studies, the dose-concentration relationship for posaconazole is highly formulation-dependent. Oral suspension demonstrates a flat dose-response with no significant concentration differences between 200 mg vs. 400 mg daily or 600 mg vs. 800 mg daily (63–67). In contrast, both the delayed-release tablet and IV formulations demonstrate a clear dose-dependent relationship: a 400 mg delayed-release tablet dose produces significantly higher concentrations than a 200 mg dose (68,69), and a 300 mg IV dose produces higher levels than 200 mg (70,71). A critical exception is noted in critically ill patients receiving oral suspension via nasogastric tube, where concentrations remain low irrespective of a 400 mg twice-daily or 200 mg four-times-daily regimen (72).
Higher serum albumin levels were significantly correlated with achieving higher posaconazole concentrations in pediatric patients (73). This finding is corroborated by a study in oncology patients using the delayed-release tablets (74). Their research specifically identified an albumin level of ≤3 g/dL as an independent risk factor associated with failing to achieve therapeutic targets both for prophylaxis (≥0.7 mg/L) and treatment (≥1.25 mg/L and ≥1.8 mg/L).
Posaconazole Dosing in Special Situations
Renal Impairment
No dose adjustment is recommended for patients with mild to moderate renal impairment. This recommendation for the suspension is based on studies showing no clinically significant difference in exposure (75) and its observed efficacy in this population (16). The same recommendation was extended to the delayed-release tablet without a dedicated clinical study (76).
The IV formulation is not recommended for patients with moderate or severe renal impairment (CrCl <50 mL/min) due to the potential accumulation of the solubilizing excipient, sulfobutyl ether-β-cyclodextrin (SBECD) (76). However, the clinical relevance of SBECD accumulation during short-term use of IV posaconazole remains uncertain. Clinicians should weigh the benefits against the potential side effects of SBECD accumulation when deciding on the use of IV posaconazole in patients with impaired renal function. Evidence from voriconazole containing SBECD suggests the risk of nephrotoxicity may be low, implying the benefit may outweigh the risk in some cases (77–79).
Hepatic Impairment
No dose adjustments are proposed for any formulation in patients with hepatic impairment (including Child-Pugh Class A, B, and C). This is based on a study of the oral suspension which found only a minor (36%) increase in AUC (80). This recommendation was directly applied to the newer tablet and IV formulations without specific studies (81).
Obesity
Patients weighing ≥120 kg are at risk of lower posaconazole exposure and may require higher doses (76). Studies confirm significantly lower concentrations in patients weighing ≥90 kg or with a BMI ≥30 (52). A population pharmacokinetic study suggested that for prophylactic use (a steady-state plasma trough concentration [Cmin ] >0.7 mg/L), a 300 mg daily dose is sufficient for patients weighing <180 kg, but a 400 mg dose is needed for those ≥180 kg. For treatment (Cmin >1.0 mg/L), 400 mg and 500 mg daily doses are recommended for patients weighing 120–170 kg and >170 kg, respectively (62).
Intensive Care Unit Patients
The oral suspension is not recommended for critically ill patients, especially via nasogastric tube due to very low and unpredictable exposure (72). The IV formulation is preferred as it shows encouraging pharmacokinetic profiles in this population, albeit with higher clearance and volume of distribution (82).
Pediatric Patients
Dosing is primarily weight-based. Higher initial dosing strategies (≥20 mg/kg/day) are recommended to achieve target concentrations for oral suspension (83,84). The delayed-release tablet is a superior choice when feasible due to better bioavailability, and model-derived dosing has shown success in achieving target levels (85).
Cystic Fibrosis
Patients with cystic fibrosis (CF) have significantly lower posaconazole concentrations. The delayed-release tablet is strongly preferred over the suspension in this population due to its satisfactory exposure (9).
Extracorporeal Membrane Oxygenation
Posaconazole exposure can be substantially compromised in extracorporeal membrane oxygenation (ECMO) patients, with ex vivo circuit data showing 63% drug loss in blood-primed ECMO circuits compared with 11% in non-ECMO controls at 24 hours (p < 0.005). Consistent with this, in vivo data from six ECMO patients showed a slow but steady rise from subtherapeutic levels to the target concentration of 1 mg/L by 48 hours, which is considered adequate for treatment. However, simulated target attainment at 48 hours was 98% for the prophylactic target (0.7 mg/L) but only 59% for the treatment target (1 mg/L). Since most, but not all, trough levels reached therapeutic thresholds, TDM can be recommended to ensure adequate exposure, particularly when higher targets are required (86).
Therapeutic Drug Monitoring of Posaconazole
Rationale and Principles of TDM
The primary rationale for TDM of posaconazole is the well-established exposure-dependent relationship with both efficacy and toxicity. Significant inter-patient variability in drug exposure occurs due to factors like formulation differences, gastrointestinal function, drug-drug interactions, and patient demographics (e.g., obesity, hypoalbuminemia). An increased risk of clinical failure and breakthrough IFIs was reported in patients with low plasma concentrations (87). For prophylaxis, Cmin of >0.7 mg/L is recommended, while a target of >1.0–1.25 mg/L is advised for treatment (27). Conversely, supratherapeutic concentrations elevate the risk of adverse drug reactions, including hepatotoxicity and posaconazole-induced pseudohyperaldosteronism (PIPH). An upper limit of 3.745 mg/L is suggested, with concentrations above 3.0 mg/L frequently linked to toxicity (88–90). Therefore, TDM aims to maintain drug levels within this therapeutic window to maximize efficacy and minimize harm.
Recommended TDM Protocol
The TDM protocol depends on the formulation. Due to its long half-life, posaconazole requires several days to reach steady state (45,87).
Oral Suspension
TDM should be performed on day 7 after initiation. However, an early level measured on day 3 has been shown to be a reliable predictor of the steady-state concentration, allowing for pre-emptive dose adjustment (61,91).
Delayed-Release Tablet and IV Formulations
These achieve steady state earlier. Therapeutic drug monitoring is recommended between days 5 and 7 of therapy (27). The gold-standard analytical method for TDM is liquid chromatography-tandem mass spectrometry (LC-MS/MS) due to its high accuracy and specificity, though other methods like bioassay are also used (87).
Indications and Frequency of TDM
Therapeutic drug monitoring is particularly crucial in specific clinical scenarios (27,87):
Treatment: For diagnosed IFIs, especially with low triazole sensitivity.
Suspected failure: To confirm adequate exposure when therapeutic efficacy is poor.
Altered absorption: In patients with gastrointestinal disorders (e.g., diarrhea, mucositis).
Adverse events: Upon emergence of suspected posaconazole-related adverse drug reactions.
Drug interactions: During concomitant use or discontinuation of drugs that affect posaconazole absorption (e.g., acid-reducing agents) or metabolism (e.g., UGT inducers like rifampicin).
Special populations: In patients with hypoalbuminemia, obesity (>120–140 kg), critical illness, or suspected poor compliance.
After the initial steady-state level, follow-up TDM should be performed following any dose adjustment or when a patient’s clinical condition changes.
Dose Adjustment Based on Therapeutic Drug Monitoring Results
Dose adjustments are guided by the trough concentration relative to the clinical target (prophylaxis >0.7 mg/L; treatment >1.0–1.25 mg/L).
The response should be a stepwise dose increase for subtherapeutic concentrations. For patients on delayed-release tablets, the dose can be increased (e.g., from 300 mg to 400 mg daily). For those on oral suspension, increasing the frequency (e.g., from 400 mg twice daily [BID] to 200 mg four times daily [QID]) or splitting doses with high-fat meals can be considered (29,92). If subtherapeutic levels persist with oral formulations, switching to the IV formulation is a highly effective strategy to ensure adequate exposure (29).
If a patient exhibits toxicity or a level significantly above the upper threshold, the dose should be reduced. Monte Carlo simulations suggest that a large proportion of patients on delayed-release tablets may maintain efficacy at a lower dose (e.g., 200 mg daily) (93).
Management in Settings Without Access to Therapeutic Drug Monitoring
In resource-limited settings without access to TDM, a proactive and preventive approach is essential. While not a substitute for TDM, these strategies can help mitigate the risks associated with unpredictable posaconazole exposure.
Formulation selection: Prioritize the use of the delayed-release tablet or IV formulations over the oral suspension, as they provide more reliable and higher drug exposure, reducing the probability of subtherapeutic levels.
Managing modifiable factors: Maximize absorption by administering the oral suspension with a high-fat meal or nutritional supplements and avoiding concomitant use of proton-pump inhibitors or H2-receptor antagonists.
Vigilant clinical monitoring: Closely monitor patients for signs of breakthrough IFIs (e.g., persistent fever, new pulmonary infiltrates) and for symptoms of toxicity (e.g., liver function test abnormalities, hypokalemia, hypertension). A high index of suspicion should prompt consideration of empirical therapy changes and diagnostic efforts.
Adhere to guidelines: Strictly follow recommended dosing regimens and contraindications regarding drug-drug interactions to minimize variability.
Posaconazole Drug Interactions
Common and Clinically Significant Interactions
Several drug combinations with posaconazole are considered contraindicated or should be strictly avoided. Concomitant use with CYP3A4-metabolized statins, such as simvastatin, lovastatin, and atorvastatin, can markedly increase statin plasma concentrations and elevate the risk of severe myopathy and rhabdomyolysis (68,94). Similarly, coadministration with ergot alkaloids may result in ergot toxicity, including vasospasm and ischemic complications (6).
A second group of interactions requires dose adjustment and close TDM. Posaconazole substantially increases exposure to calcineurin inhibitors, particularly tacrolimus and cyclosporine, through CYP3A4 inhibition (95). In addition, posaconazole increases systemic exposure to benzodiazepines, especially oral midazolam, potentially leading to excessive sedation and respiratory depression (96).
Posaconazole is also associated with frequent clinically relevant interactions that warrant heightened vigilance. Concomitant use with QT-prolonging agents including antiarrhythmics (e.g., amiodarone), fluoroquinolones, macrolides, and certain antipsychotics may increase the risk of QT prolongation and torsades de pointes (TdP), and electrocardiographic monitoring is recommended (97). Furthermore, posaconazole may increase plasma concentrations of direct oral anticoagulants (DOACs), such as apixaban and rivaroxaban, thereby increasing bleeding risk; in high-risk patients, low-molecular-weight heparin may represent a safer alternative. Interactions with sulfonylureas have also been reported and may result in hypoglycemia (98).
Conversely, several drugs can reduce posaconazole exposure and compromise antifungal efficacy. Acid-suppressive agents, including proton pump inhibitors and H2-receptor antagonists, significantly impair absorption of the oral suspension formulation. Co-administration of proton pump inhibitors and steroids may be a risk factor for low trough concentrations of posaconazole delayed-release tablets in adult patients with hematological malignancies. Increased gastrointestinal motility induced by agents such as metoclopramide may further reduce systemic exposure (99). Potent enzyme inducers, including rifampicin, phenytoin, carbamazepine, and efavirenz, markedly decrease posaconazole plasma concentrations and are therefore contraindicated (100).
Interactions with Chemotherapeutic Agents, Immunosuppressants, and Targeted Therapies
Vinca Alkaloids
Interactions between vinca alkaloids and azole antifungals are well documented. Vincristine disrupts mitosis by binding to microtubular proteins, particularly tubulin, and is metabolized by CYP3A4 and transported by P-gp (101). Triazole antifungals inhibit vincristine metabolism via CYP3A4, and posaconazole additionally inhibits P-gp-mediated transport (102). Consequently, posaconazole significantly increases exposure to vincristine and vinblastine, leading to severe neurotoxicity, autonomic dysfunction, paralytic ileus, and syndrome of inappropriate antidiuretic hormone secretion (SIADH). Concomitant use should be avoided, and alternative antifungal agents should be considered when vinca alkaloids are administered (101).
Calcineurin Inhibitors
Posaconazole markedly increases exposure to calcineurin inhibitors, particularly tacrolimus and cyclosporine, necessitating pre-emptive dose reduction and intensive TDM. Cyclosporine, widely used for graft rejection prophylaxis and GVHD management, is extensively metabolized via CYP3A4. Coadministration with posaconazole increases cyclosporine bioavailability, requiring dose reductions of approximately 14–29% (95,101). Tacrolimus, metabolized by CYP3A4 and subject to intestinal first-pass metabolism, shows pronounced increases in exposure when combined with posaconazole. Reported increases include a threefold rise in AUC and up to 121% and 358% increases in Cmax and AUC, respectively, necessitating dose reductions of 50–70%. Retrospective data from bone marrow transplant recipients indicate a mean tacrolimus dose reduction of approximately 13% with posaconazole to maintain therapeutic levels (101,103,104).
Mammalian Target of Rapamycin Inhibitors
Sirolimus binds FK506-binding protein 12 (FKBP12) to inhibit mammalian target of rapamycin (mTOR), a key regulator of cell cycle progression. Concomitant administration with posaconazole markedly increases sirolimus exposure and often requires a 60–80% dose reduction. Due to the magnitude of this interaction, some regulatory agencies contraindicate combined use, as posaconazole 200 mg has been shown to increase sirolimus Cmax and AUC by 527% and 788%, respectively (101,105).
BCL-2 Inhibitors
Venetoclax, a BCL-2 inhibitor metabolized by CYP3A4 and used in chronic lymphocytic leukemia (CLL) and AML, has one of the most clinically significant interactions with posaconazole. Coadministration may increase venetoclax exposure more than fivefold, substantially increasing the risk of tumor lysis syndrome and severe cytopenias. Mandatory dose reductions (often ≥75%) and close monitoring are required, and this interaction is frequently addressed in institutional protocols (106).
Kinase Inhibitors and Bruton’s Tyrosine Kinase Inhibitors
Many tyrosine kinase inhibitors (TKIs), including FLT3 inhibitors (midostaurin, gilteritinib) and BTK inhibitors (ibrutinib), are CYP3A4 substrates. Posaconazole coadministration may substantially increase drug exposure, leading to enhanced toxicity such as QT prolongation, hepatotoxicity, or myelosuppression. Management strategies depend on the targeted agent’s therapeutic window.
Midostaurin, a multikinase inhibitor targeting FLT3, KIT, platelet-derived growth factor receptor (PDGFR), vascular endothelial growth factor receptor 2 (VEGFR2), and protein kinase C (PKC) family kinases, is approved for FLT3-mutated AML and advanced systemic mastocytosis. It has an elimination half-life of approximately 21 hours, and coadministration with posaconazole has been associated with up to an eightfold increase in exposure (101,107,108).
Gilteritinib, an FLT3 and AXL inhibitor, is metabolized by CYP3A4 and is a substrate of P-gp and breast cancer resistance protein (BCRP). Strong inhibitors of these pathways, including posaconazole, may significantly increase gilteritinib plasma concentrations. Alternative agents should be used when possible; otherwise, careful toxicity monitoring is required (101,109).
Ibrutinib, a BTK inhibitor used in mantle cell lymphoma, CLL, and Waldenström macroglobulinemia, is predominantly metabolized by CYP3A4. Strong CYP3A4 inhibitors, including posaconazole, should generally be avoided. If unavoidable, dose reduction to 140 mg or temporary interruption (≤7 days) is recommended, with close monitoring for toxicity (101,110).
Immune Checkpoint Inhibitors
Immune checkpoint inhibitors targeting cytotoxic T-lymphocyte-associated protein 4 (CTLA-4), programmed cell death protein 1 (PD-1), or programmed death-ligand 1 (PD-L1) do not exhibit direct pharmacokinetic interactions with posaconazole. However, overlapping toxicities, particularly hepatotoxicity, may complicate clinical assessment. Additionally, immunomodulation may influence susceptibility to invasive fungal infections, underscoring the need for careful clinical monitoring rather than dose modification (111).
Chimeric Antigen Receptor T-Cell Therapy and B-Cell-Depleting Bispecific Antibodies
Chimeric antigen receptor T-cell therapies and B-cell-depleting bispecific antibodies are not subject to metabolic interactions with posaconazole. Nevertheless, these therapies are associated with prolonged cytopenias, hypogammaglobulinemia, and immune dysregulation, increasing the risk of invasive fungal infections. Posaconazole is frequently used for prophylaxis in this setting, but clinicians should remain vigilant for additive hepatotoxicity and difficulty distinguishing drug-related adverse effects from therapy-related complications such as cytokine release syndrome or immune effector cell-associated neurotoxicity syndrome (ICANS) (112–114).
Spectrum of Activity and Susceptibility
In vitro Activity of Posaconazole: Overview
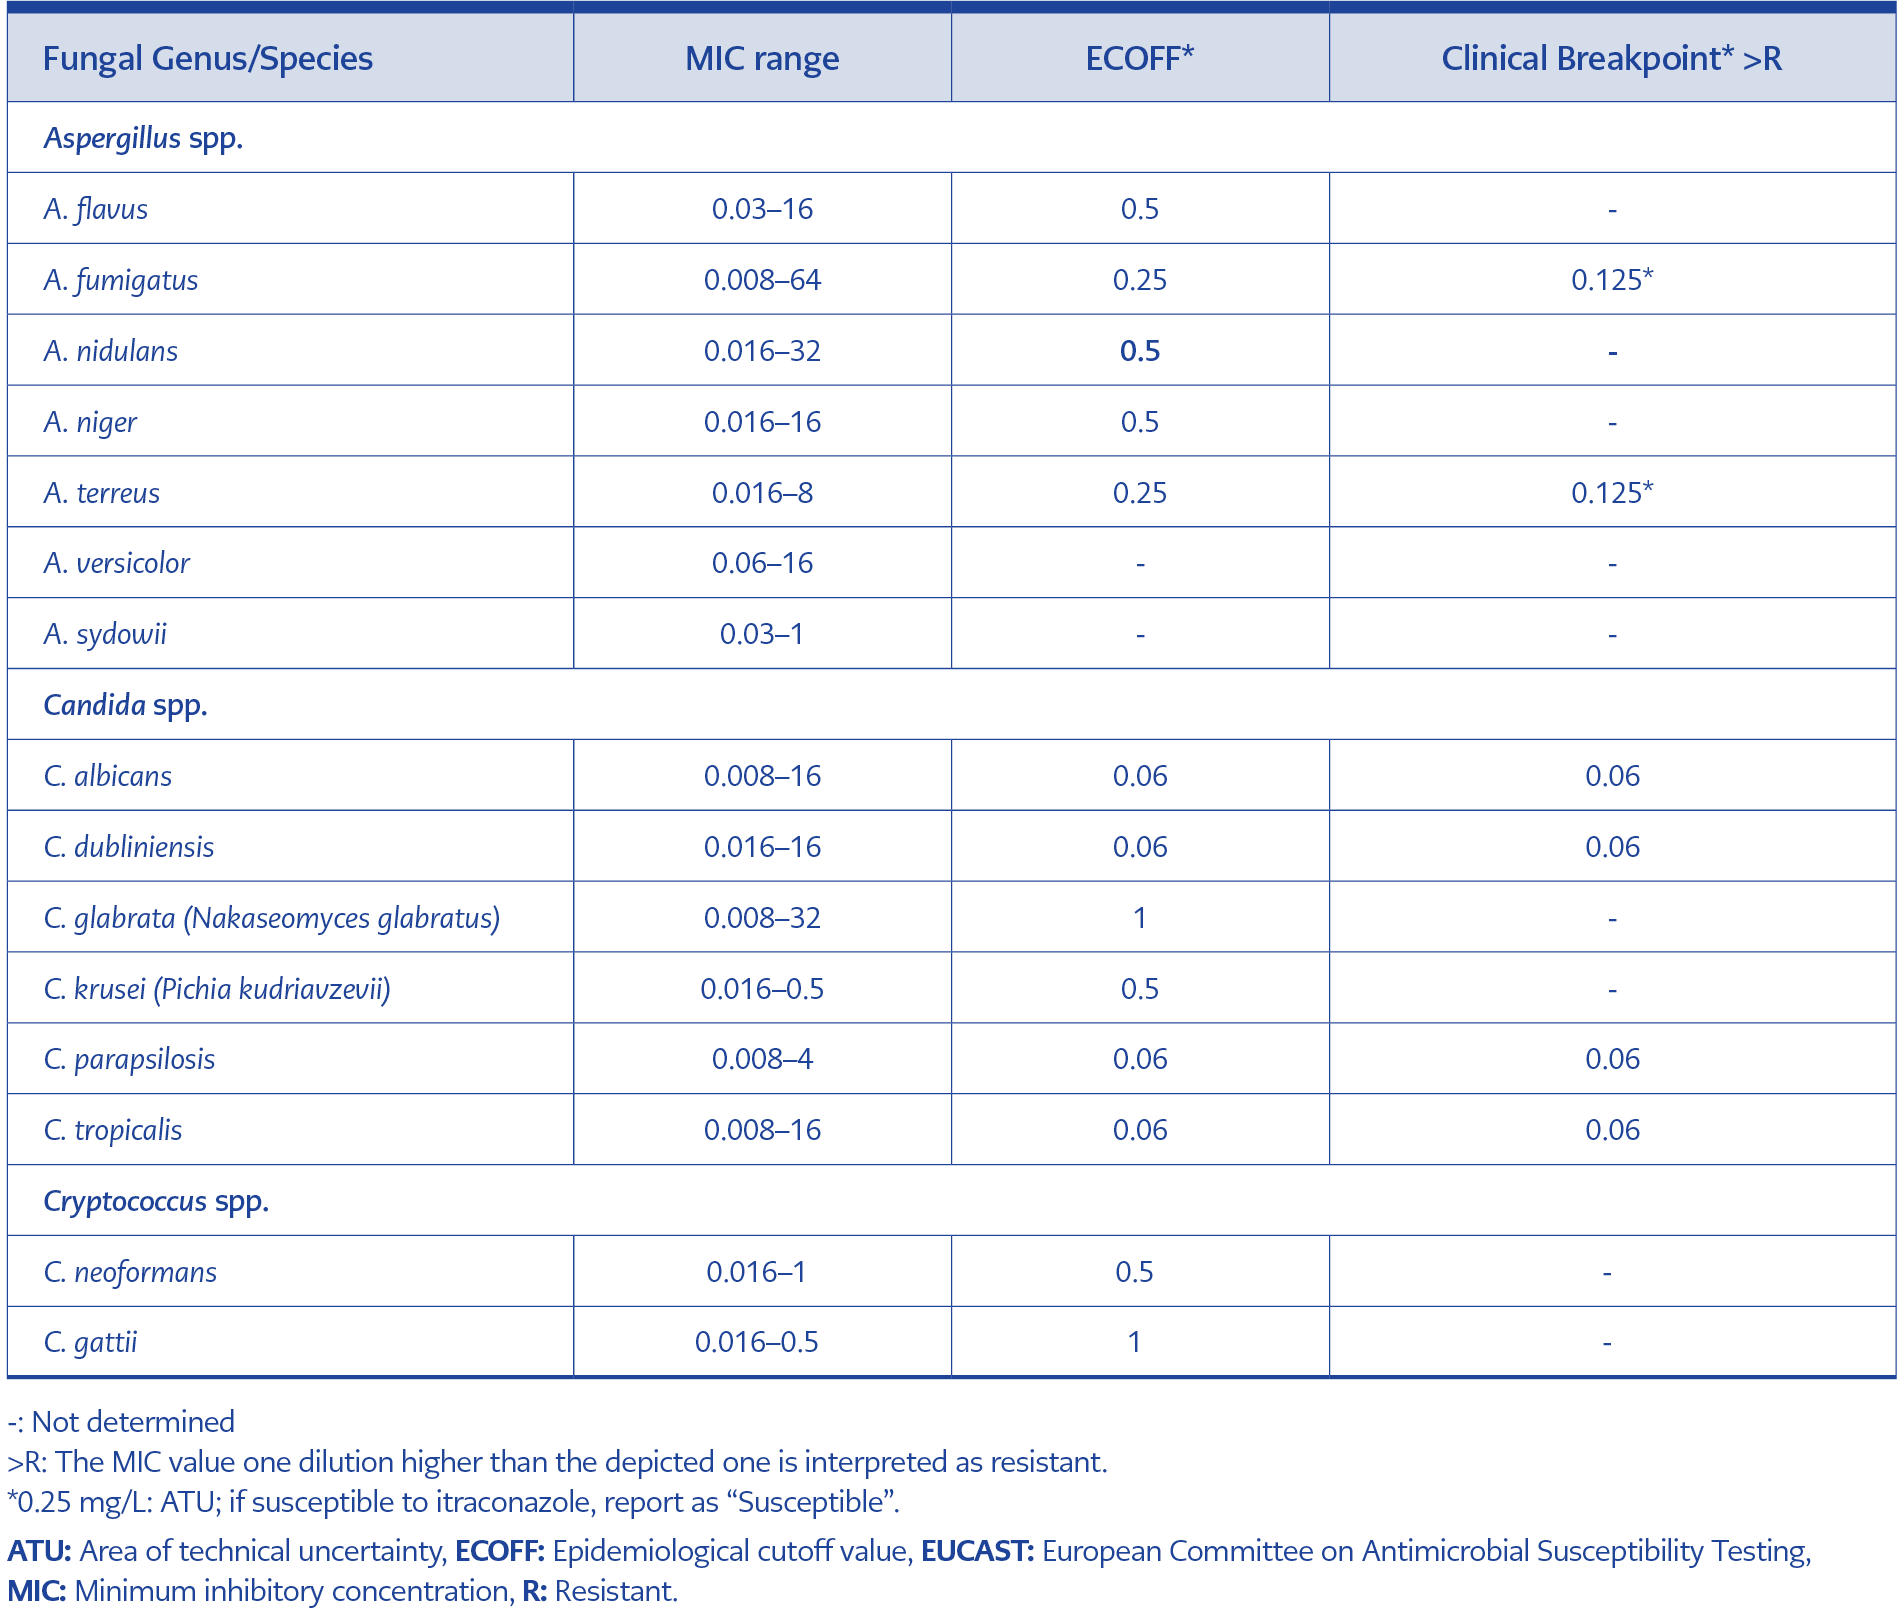
Table 2. Minimum inhibitory concentration (MIC) ranges, epidemiological cut-off values (ECOFF) (mg/L), and clinical breakpoints assessed by the EUCAST reference microdilution method for posaconazole using combined distributions from multiple sources and time periods and against fungi commonly encountered in invasive human infections (126).
Available reference antifungal susceptibility testing methods render the assessment of the degrees of in vitro activity possible against various fungal genera and species, including yeasts, molds, and dermatophytes (6,115–123). Posaconazole is active against Candida, Cryptococcus, Aspergillus, Mucorales, and some endemic thermally dimorphic fungi (mainly Blastomyces dermatitidis, Coccidioides immitis, and Histoplasma capsulatum). Its activity against dimorphic fungi is fungistatic and lower against Sporothrix schenckii (124). Posaconazole may exert some activity against certain rare yeasts (Rhodotorula, Trichosporon) and rare molds, including Fusarium. Although the susceptibility may vary depending on the species, it exerts a high degree of activity against dematiaceous molds (124,125). Available clinical breakpoints determined using the method of the European Committee on Antimicrobial Susceptibility Testing (EUCAST) are depicted in Table 2. The spectrum and degree of the in vitro activity of posaconazole against specific fungal genera and species are outlined in detail below and in Table 3 (123,126,127).
Yeasts: Candida Species
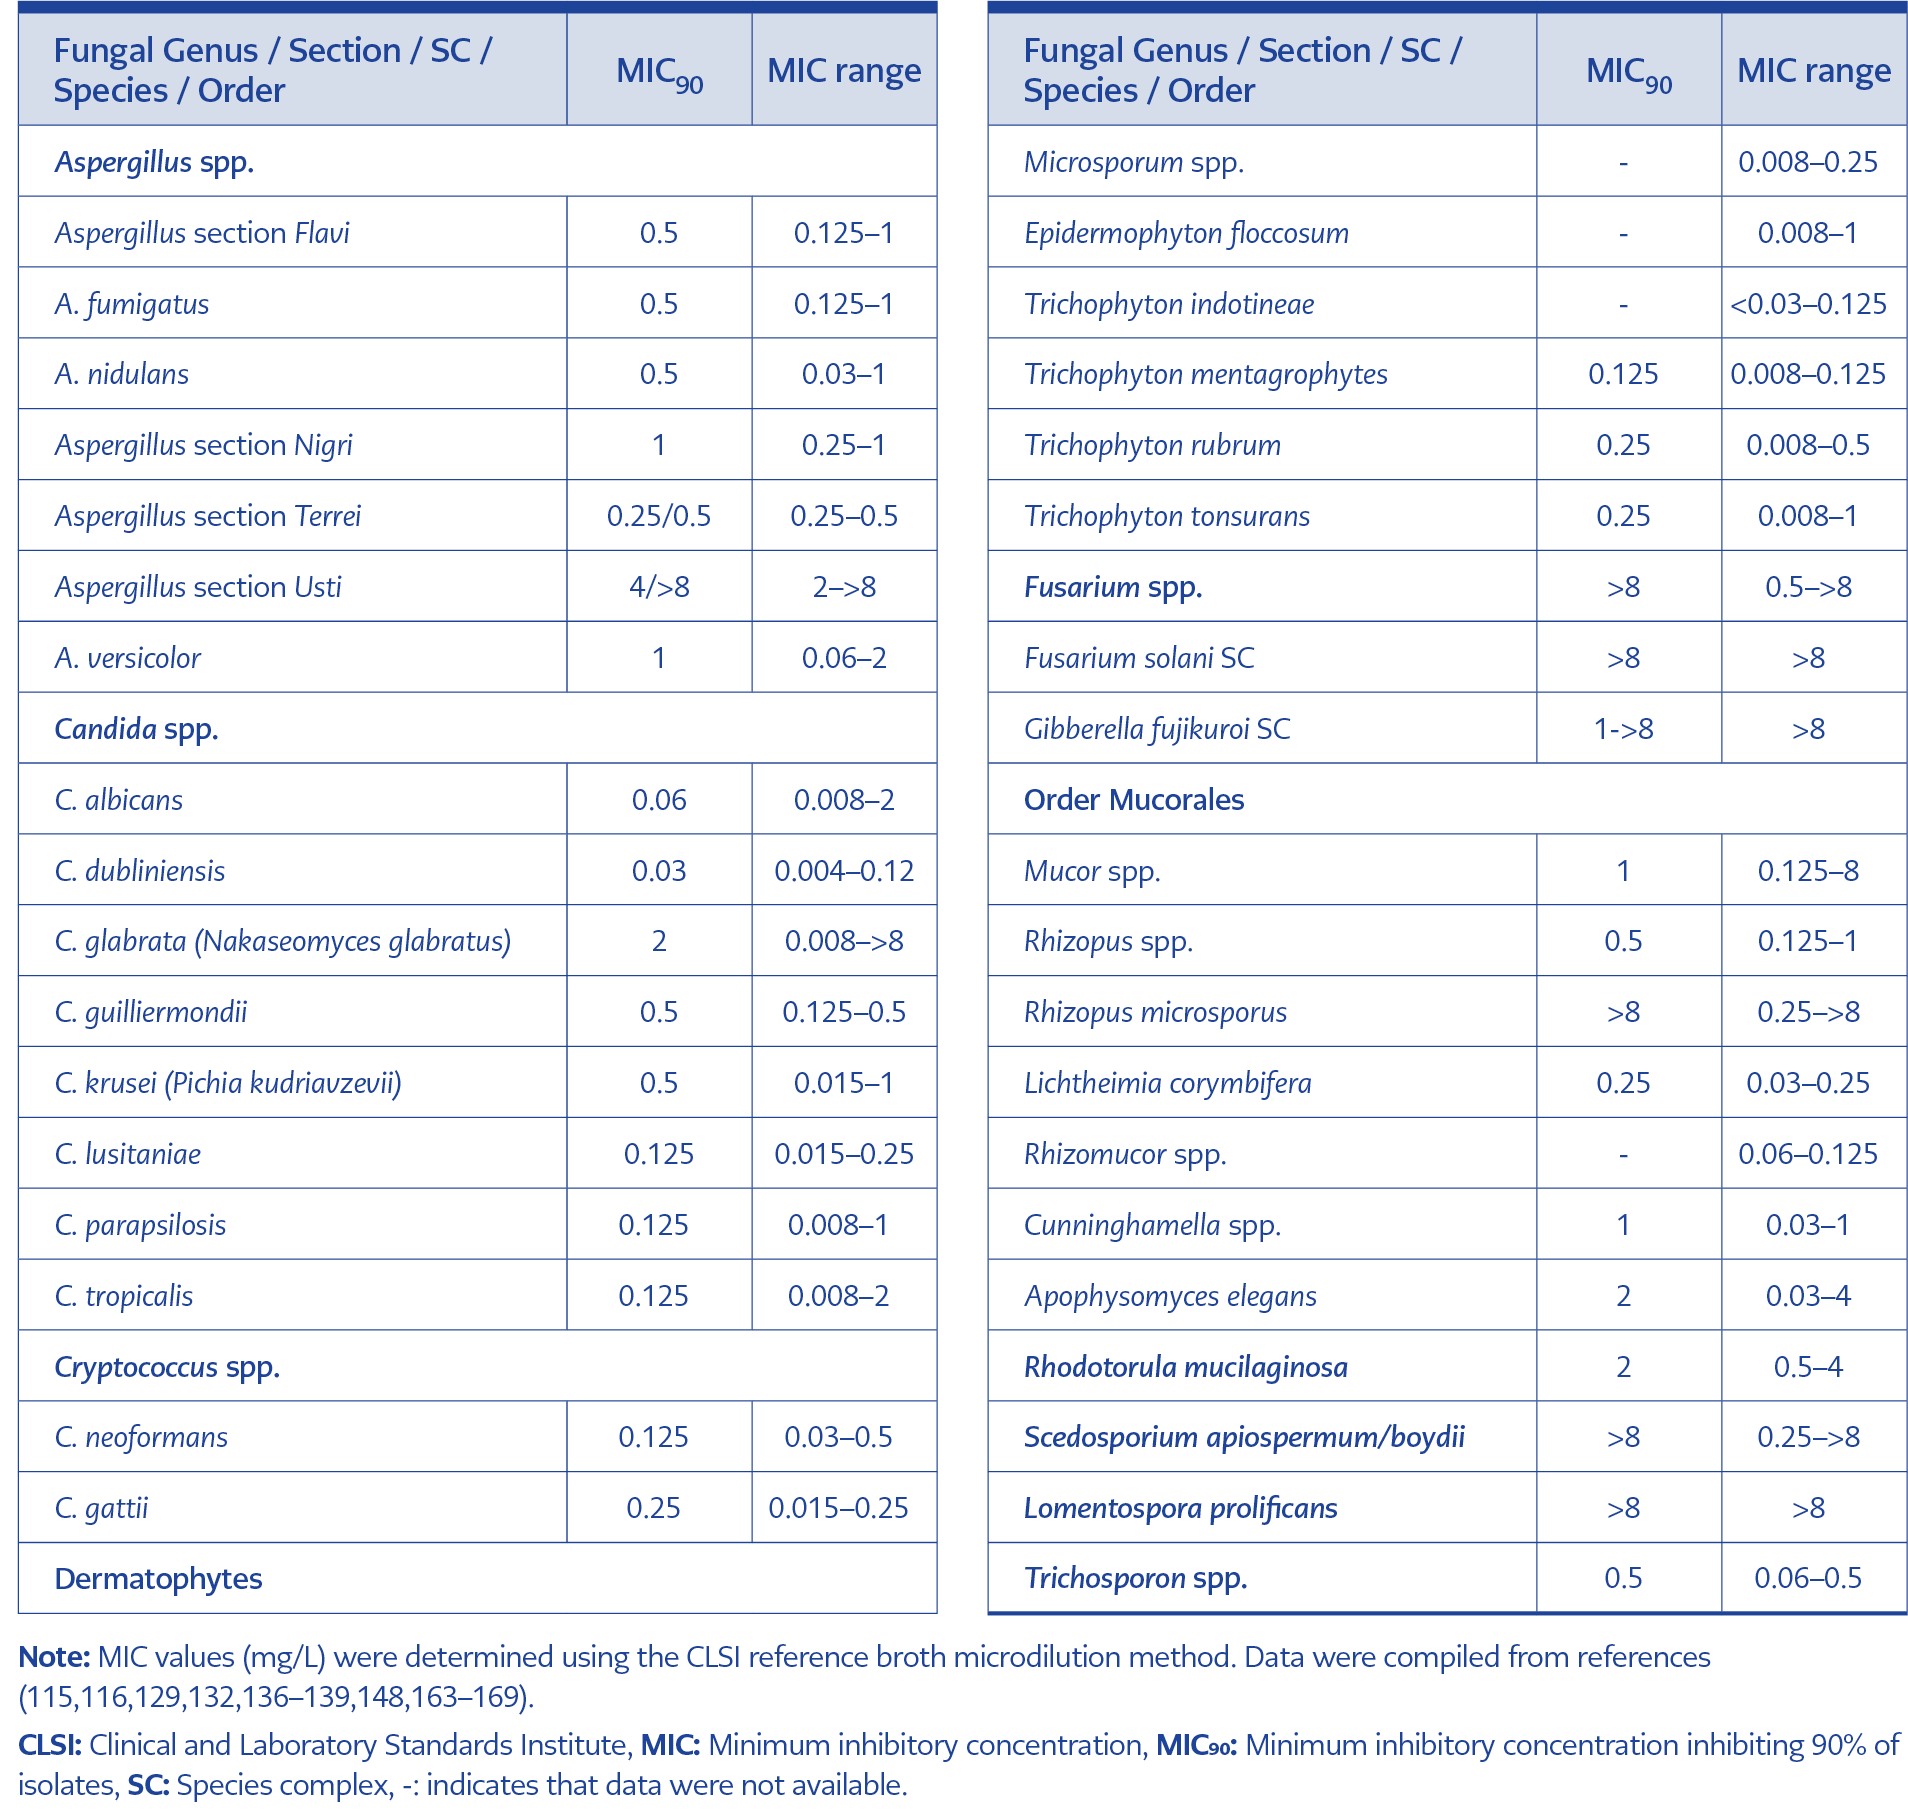
Table 3. In vitro activity of posaconazole against clinically relevant fungi.
Posaconazole exhibits in vitro activity against various Candida species. However, the degree of its activity is not uniform across different species. Azole resistance is detected in some clinical Candida isolates of various species, and the resistance pattern may involve more than one azole, including posaconazole, based on the possibility of azole cross-resistance in a set of isolates. Due to the extended structure of posaconazole, additional binding domains on the target enzyme, and a lower affinity for efflux pumps, posaconazole may retain activity against some strains resistant to other azoles (128). Relatively higher posaconazole minimum inhibitory concentrations (MICs) are expected for fluconazole-resistant strains (126,129,130) (Tables 2 and 3). In a multicenter study in Türkiye of candidemia isolates collected between 1997 and 2017, posaconazole non-wild-type (WT) isolates were detected among strains of Candida parapsilosis and Candida krusei at rates of 3.5 and 1.9%, respectively, using the Clinical and Laboratory Standards Institute (CLSI) reference microdilution method (131).
Posaconazole activity against yeasts is mostly fungistatic (124). Fungicidal activity against some Candida spp. and Cryptococcus neoformans has also been detected (132,133).
Rare Yeasts
While in vitro activity data have been reported, adequate clinical data regarding efficacy of posaconazole against non-Candida yeast infections, including those due to Cryptococcus, are lacking, and there is no licensed indication (126). In vitro, posaconazole is more potent than amphotericin B and fluconazole against Cryptococcus, with lower minimum inhibitory concentration (MIC) values. Posaconazole MICs tended to be higher for fluconazole-resistant C. neoformans isolates as compared to those for fluconazole-susceptible ones due to cross-resistance (134).
A head-to-head comparison of the in vitro activities of fluconazole, itraconazole, voriconazole, posaconazole, and isavuconazole against strains of Trichosporon asahii isolated in a tertiary care center in Türkiye showed that all tested triazoles were fungistatic and the most active triazole was voriconazole (MIC90: 0.5 mg/L). This was followed by itraconazole (MIC90: 2 mg/L), posaconazole (MIC90: 2 mg/L), and isavuconazole (MIC90: 1 mg/L), displaying similar activities to each other. Fluconazole exerted limited and the least activity (MIC90: 32 mg/L) (135). In vitro activity of posaconazole against Rhodotorula may remain moderate to limited, with relatively lower MICs for some isolates (Table 3). MIC90 values for posaconazole, voriconazole, fluconazole, and amphotericin B against isolates of Rhodotorula mucilaginosa (2, 2, >64, and 1 mg/L, respectively) suggested more potent in vitro activity of amphotericin B than posaconazole and voriconazole. Fluconazole did not exert any antifungal effect (136).
Aspergillus Species
Posaconazole is active in vitro against Aspergillus spp., and the degree of activity is generally similar across species (Table 3) (126,137). Importantly, secondary posaconazole resistance may be observed together with varying combinations of other azole compounds, itraconazole, voriconazole, and isavuconazole (126). In the SENTRY Antifungal Surveillance Program (2018–2021) for isolates causing invasive mold infections, posaconazole susceptibility rates were detected as 95.5–100% in Aspergillus strains. Most Aspergillus strains were WT for posaconazole (Aspergillus fumigatus, 97.3% WT, Aspergillus section Nigri, 100% WT, Aspergillus section Flavi, 99.2% WT, and Aspergillus section Terrei, 100% WT). Posaconazole was not active against Aspergillus section Usti (Aspergillus calidoustus) (MIC90: 4/>8 mg/L) (Table 3) but displayed activity against Aspergillus lentulus (MIC: 0.5 mg/L) and Aspergillus thermomutatus (MIC: 1 mg/L) (138–140).
The prevalence of secondarily azole-resistant A. fumigatus strains has increased over the last two decades due to long-term use of azole treatments, especially in particular patient populations and the use of azole fungicides in agriculture (130). Global surveillance data suggest widely varying rates of azole resistance among clinical and environmental A. fumigatus strains (119). Depending on the molecular mechanism of resistance and the specific mutation identified, posaconazole resistance may also be observed among these azole-resistant isolates. In a prospective multicenter study conducted in Türkiye, 358 clinical strains of A. fumigatus isolated in May 2018 to May 2019 were tested, and azole resistance was detected in 11 (3.1%) of the strains. Of the 11 azole-resistant isolates, four were resistant to posaconazole, all of which were also resistant to itraconazole and voriconazole (141).
The available EUCAST agar screening method for detecting azole resistance among Aspergillus strains, exemplified by A. fumigatus, is a practical method for initial detection of resistance to posaconazole, itraconazole, and voriconazole and should be followed by the reference microdilution method to confirm resistance (6,122).
Secondary azole resistance among isolates of other Aspergillus sections, including Aspergillus section Flavi, has also emerged, though with fewer reports and studies. The rate of non-WT A. flavus isolates for posaconazole was 5.1% (and 0.8 and 1.7% for itraconazole and voriconazole, respectively) (142,143).
Primarily based on the different mechanism of action and, importantly, the in vitro activity of posaconazole remained similar against amphotericin B-resistant Aspergillus strains as compared to that against amphotericin B-susceptible strains (144).
Mucorales
Because most isolates in previously published reports and because few strains were analyzed, most assessments for in vitro activity of antifungal drugs remain at the genus level for isolates of the order Mucorales (Table 3). Also, and importantly, clinical breakpoints remain undetermined, and isolates can be categorized as WT or non-WT only using the available CLSI epidemiological cutoff values (ECV). Together with amphotericin B and isavuconazole, posaconazole is one of the antifungal agents that displays activity against the order Mucorales. However, the activities of all three of these drugs remain suboptimal, and there is an unmet need for novel therapeutic strategies for mucormycosis (145). While posaconazole is used for salvage treatment of patients with mucormycosis refractory to prior antifungal therapy or for patients intolerant of other antifungal regimens, its activity in vitro remains variable against genera/species in order Mucorales with slightly lower activity against Mucor circinelloides and the determined ECV for CLSI reference microdilution method (available for Lichtheimia corymbifera, M. circinelloides, Rhizopus arrhizus, and Rhizopus microsporus) is one dilutionhigher for this species (4 mg/L) as compared to that for other species (2 mg/L for Rhizopus arrhizus, R. microsporus, and L. corymbifera) in order Mucorales (146). Based on the generated MICs, in general, posaconazole was found to be active against L. corymbifera, Rhizomucor pusillus, R. arrhizus, and Cunninghamella spp., but did not show activity against some isolates of Mucor (Table 3).
Dermatophytes
Posaconazole is active against the dermatophytes Microsporum, Epidermophyton, Trichophyton, and the posaconazole MIC values are shown in Table 3. Based on the generated MIC values, in vitro activity of posaconazole against dermatophytes is similar to or superior to itraconazole (147,148).
The US Food and Drug Administration (FDA) approved posaconazole for the clinical use of invasive aspergillosis, oropharyngeal candidiasis, itraconazole- and fluconazole-resistant oropharyngeal candidiasis, and prophylaxis for invasive Aspergillus and Candida infections, but not onychomycosis or superficial fungal infections. Based on its favorable in vitro activity against dermatophytes, posaconazole has been reported to be used off-label to treat dermatophytic skin and nail infections and may be considered a second-line agent, particularly in patients resistant or intolerant of terbinafine (149,150).
The in vitro activity of posaconazole against Trichophyton indotineae has attracted particular interest because this novel dermatophyte species shows terbinafine resistance. Mutations in the squalene epoxidase gene and related amino acid changes (Leu393Phe, Phe397Leu) commonly cause terbinafine resistance, and alternative therapeutic regimens are often required (151).
Rare Molds
Posaconazole shows limited, species-specific, variable, and fungistatic in vitro activity against Fusarium spp. (124). In one study, the Fusarium strains most susceptible to posaconazole in vitro were Fusarium moniliforme and Fusarium oxysporum (Fusarium solani MIC90: 32 mg/L vs. F. oxysporum: 2 mg/L and F. moniliforme: 1 mg/L by CLSI reference microdilution method) (123). Posaconazole does not exert antifungal effect against Lomentospora prolificans, Rasamsonia argillacea, Microascus cirrosus, Sarocladium kiliense and Scopulariopsis spp. Its activity is limited against Scedosporium (Table 3) (127,138). Testing posaconazole against 30 strains of Pseudallescheria boydii by the CLSI reference microdilution method yielded MIC90 values of 1 mg/L and 4 mg/L for posaconazole and itraconazole, respectively, suggesting better in vitro activity of posaconazole than itraconazole against P. boydii (152).
Activity in Experimental Animal Models
In experimental models of various IFIs, posaconazole proved to be effective and possess antifungal activity in treatment of invasive aspergillosis (153), mucormycosis (154), fusariosis caused by F. solani (155), cerebral phaeohyphomycosis caused by Ramichloridium mackenziei (156), histoplasmosis (157), blastomycosis (158), and coccidioidomycosis (159,160) in murine models, as well as in experimental cryptococcal meningitis in a rabbit model (133). Notably, although posaconazole appeared active in the rabbit cryptococcal meningitis model, no drug levels were detected in cerebrospinal fluid (133).
Resistance Mechanisms and Trends
Multiple mutations in the ERG11 gene, which encodes the lanosterol demethylase enzyme, were required to reduce susceptibility to posaconazole in Candida albicans strains (124). Point mutations in the cyp51 gene, which encodes lanosterol 14-α-demethylase, and cyp51 overexpression (tandem repeats in the promoter and transcription factor regulation) are major mechanisms of azole resistance in Aspergillus. Overexpression of multidrug efflux pumps (ABC and MFS transporters) and biofilm formation may also contribute to resistance development (119,161).
In analyses of A. fumigatus isolates with itraconazole, posaconazole, or voriconazole MIC values above the ECVs, alterations in cyp51A or cyp51B were detected as a major mechanism of posaconazole resistance (138,139). Among the cyp51A-mediated mechanisms of azole resistance in A. fumigatus, some of the mutations and related modifications observed to be associated with posaconazole resistance are G54 (itraconazole and posaconazole resistance and variable voriconazole susceptibility), G138 (pan-azole resistance), G448 (variable posaconazole susceptibility, itraconazole, voriconazole, and isavuconazole resistance), M220 (itraconazole and posaconazole resistance, variable voriconazole and isavuconazole susceptibility), TR34/L98H (itraconazole and posaconazole resistance, variable voriconazole and isavuconazole susceptibility), and TR46/Y121F/T289A (voriconazole and isavuconazole resistance, variable itraconazole and posaconazole susceptibility) (162). Azole-resistant isolates with WT cyp51A genotype are also being detected, making whole-genome sequencing significant (119,141).
Safety Profile of Posaconazole and Adverse Effects
Posaconazole is generally regarded as safe and well-tolerated, but its clinical use requires careful monitoring. This is primarily due to a spectrum of adverse events (AEs) ranging from mild gastrointestinal disturbances to severe hepatic and cardiac complications. Clinical data, primarily from oral suspension studies, show that treatment-emergent AEs occur in 38–57% of cases, a frequency similar to placebo and active comparators (10,11,18).
Most adverse events reported with posaconazole were mild, self-limiting, and non-specific. Discontinuation of treatment in healthy adults due to drug adverse effects is reported to be less than 1%, with serious adverse effects occurring at a rate of 0.7% (18). In clinical trials, treatment-related serious adverse events occurred in 6–13% of patients, similar to control groups, which ranged from 2–10% (10,11). A high rate of treatment discontinuation was reported in a prophylaxis study due to the severity of the underlying disease; only 46% of patients in the posaconazole group and 41% in the comparator group completed the full treatment (11).
The most reported adverse reactions, generally mild to moderate and consistent across all formulations, include gastrointestinal issues (8–11%, such as diarrhea, nausea, vomiting, abdominal pain) and laboratory changes (1–4%, such as mild to moderate elevations in liver function tests) (8,10,11,170). In a multicenter study from Türkiye, 115 patients with AML receiving posaconazole oral suspension prophylaxis reported gastrointestinal adverse events, including nausea (32.2%), vomiting (10.4%), and diarrhea (15.7%) (171).
Critical safety concerns involve hepatotoxicity, QTc prolongation, and cardiac arrhythmias, which necessitate careful monitoring. Severe, and occasionally fatal, hepatic reactions have been documented, particularly in patients with complex underlying comorbidities (172). Consequently, baseline and periodic liver function tests are mandatory, with drug cessation required if significant abnormalities emerge (76). Furthermore, as an azole class effect, posaconazole may induce QTc interval prolongation, heightening the risk of life-threatening arrhythmias such as TdP. This risk is exacerbated by concurrent electrolyte imbalances (hypokalemia, hypomagnesemia, or hypocalcemia), which must be corrected before initiating therapy (9,76). The incidences of treatment-related atrial fibrillation and TdP are less than 1% (10).
Posaconazole is a potent inhibitor of the liver enzyme CYP3A4, which metabolizes many other drugs, potentially leading to dangerously high concentrations of co-administered medications (see the Drug Interactions section for details).
Other uncommon, non-serious side effects include systemic symptoms (headache, fatigue, fever), hematologic effects (including thrombocytopenia, neutropenia, and anemia), and hypersensitivity (including rash, urticaria, and angioedema). Although posaconazole has been favored as an alternative treatment for patients who develop phototoxic effects on voriconazole (173), photosensitivity related to posaconazole has been reported (174). Patients should be advised to avoid sun exposure or use protective measures.
Pseudohyperaldosteronism, a rare but clinically significant condition characterized by new-onset or refractory hypertension accompanied by abnormal laboratory findings (hypokalemia, low serum renin and aldosterone, and elevated 11-deoxycortisol), has been reported after posaconazole use in the postmarketing surveillance (175,176).
Severe reactions including seizures, peripheral neuropathy, and paralytic ileus have occurred when posaconazole is used concurrently with vincristine, due to increased vincristine levels (76). Blurred vision, photophobia, reduced visual acuity, visual hallucinations, and neurological disturbances were also reported with posaconazole use (177).
The inherent safety risks (hepatotoxicity, QTc prolongation, and drug interactions) are consistent across all forms; however, the specific formulation significantly affects the absorption, drug-level consistency, and the risk of subtherapeutic levels, which in turn affects overall safety and efficacy (10,172).
The specific drug formulation further influences the safety profile. The IV formulation utilizes SBECD as a solubilizing agent. Due to the potential for SBECD accumulation, the IV route is generally avoided in patients with moderate to severe renal impairment unless the clinical necessity outweighs the risks (76). If used, serum creatinine levels must be monitored closely. If creatinine increases, a switch to an oral formulation should be considered. Pain, phlebitis and thrombosis-like infusion-site reactions were each reported by less than 1% of patients during IV posaconazole treatment (10).
Posaconazole is contraindicated in persons with known hypersensitivity to posaconazole or any component of the formulation. The delayed-release oral suspension contains sorbitol, so it is contraindicated in patients with hereditary fructose intolerance (76).
Based on animal data, it may cause fatal harm when administered to pregnant women. Human data on the use of posaconazole during pregnancy are insufficient, and its safety during lactation is not established, so it should be avoided during lactation (76).
Posaconazole in the Antifungal Prophylaxis
Posaconazole is widely used for the prophylaxis of IFIs in high-risk, immunocompromised patients. Its use is supported by major clinical guidelines, including those from the IDSA and the National Comprehensive Cancer Network (NCCN). Additionally, the ECIL recommends it, a joint venture of the European Group for Blood and Marrow Transplantation (EBMT), the European Organization for Research and Treatment of Cancer (EORTC), the Immunocompromised Host Society (ICHS), and the European LeukemiaNet (ELN) (13,14).
Primary Antifungal Prophylaxis
Primary antifungal prophylaxis refers to using an antifungal agent to prevent an initial IFI in a high-risk patient. Posaconazole has been a cornerstone of this strategy, particularly in patients with AML receiving induction chemotherapy and those undergoing HSCT with GVHD (13,14,178–182).
Following administration of posaconazole prophylaxis in AML patients, the number of febrile days, the incidence rate of invasive fungal diseases (IFDs) and aspergillosis, and the length of hospital stay were significantly reduced (183).
Indications in Hematologic Malignancies and Hematopoietic Stem Cell Transplantation
Posaconazole is strongly recommended for primary antifungal prophylaxis in two key patient populations:
Patients with AML or MDS: It is indicated for patients undergoing induction or re-induction chemotherapy that is expected to cause prolonged and severe neutropenia (179,180,184–186).
Allogeneic HSCT Recipients: It is indicated for patients who are at high risk for invasive aspergillosis, particularly those with GVHD receiving intensive immunosuppressive therapy (11,187–189).
In these patient groups, posaconazole prophylaxis has significantly reduced the incidence of IFIs and, in some cases, improved overall survival.
Special Considerations in Allogeneic Stem Cell Transplantation
Posaconazole is effective and generally well-tolerated in allogeneic HSCT, but drug-drug interactions (notably with sirolimus and cyclosporine) require careful monitoring and dose adjustments (190). Therapeutic drug monitoring is advised in cases of suspected breakthrough infection or absorption issues (30,87).
In allogeneic HSCT, patients are at a particularly high risk for IFIs due to the profound and prolonged immunosuppression. Posaconazole prophylaxis is crucial in this setting, especially in those with GVHD. The duration of prophylaxis is often extended until immunosuppression is significantly reduced. Therapeutic drug monitoring is often recommended to ensure adequate drug levels, especially in patients with GVHD who may have issues with oral absorption (11).
Prophylaxis in Viral-Associated Fungal Infections
Posaconazole may be considered for prophylaxis against invasive pulmonary aspergillosis (IPA), including in the context of viral-associated fungal infections such as influenza-associated pulmonary aspergillosis (IAPA) and COVID-19-associated pulmonary aspergillosis (CAPA), especially in immunocompromised patients. However, breakthrough infections can occur, including with resistant or less susceptible fungi (e.g., Mucorales) (191).
In recent years, IPA has been increasingly recognized in critically ill patients with viral pneumonitis. The most common manifestations are influenza-associated pulmonary aspergillosis (IAPA) and CAPA. Both conditions are associated with high mortality, even though most affected patients were previously immunocompetent. While the exact mechanisms underlying IAPA and CAPA remain incompletely understood, their development involves complex interactions among viral, fungal, and host factors. Because patients may exhibit different patterns of immune dysfunction—ranging from excessive inflammation to immune suppression—accurately identifying the dominant immune state is essential for choosing appropriate host-targeted therapies. Although IAPA and CAPA share pathogenic features such as airway epithelial injury and excessive inflammation, they differ in other underlying mechanisms. Effective management of IAPA and CAPA should therefore extend beyond antiviral and antifungal treatment to include host-directed therapies aimed at restoring immune balance (192,193).
Posaconazole Prophylaxis for COVID-19-Associated Pulmonary Aspergillosis
Early in the pandemic, high CAPA incidence and mortality prompted off-label posaconazole prophylaxis in ventilated COVID-19 patients receiving high-dose steroids. However, experience revealed a critical flaw: the oral suspension yielded very low trough levels, rendering TDM ineffective (194,195).
Subsequent studies produced conflicting results. A three-center case-control study found that prophylaxis efficacy depended heavily on center-specific CAPA baseline incidence, with benefit only seen in high-prevalence settings (196). While mold-active antifungal prophylaxis consistently reduced CAPA incidence—one study reported a hazard ratio of 0.08, and a monocentric cohort observed all CAPA cases in the non-prophylaxis group—this reduction did not translate into survival benefit (192).
A systematic review and meta-analysis of nine intensive care unit (ICU)-based studies including 1321 patients evaluated antifungal prophylaxis (inhaled amphotericin B or systemic posaconazole) versus standard care in COVID-19 patients. Prophylaxis significantly reduced CAPA incidence (relative risk (RR) 0.21, 95% confidence interval (CI) 0.14–0.33; p < 0.001), with consistent benefit for inhaled amphotericin B (RR 0.18, p = 0.001) but variable results for posaconazole. However, no significant effects were observed on mortality, time to CAPA onset, or ICU length of stay. Efficacy was most pronounced in mechanically ventilated patients and retrospective cohorts. While these findings support a potential role for prophylaxis in reducing CAPA risk, the lack of survival benefit and the need for direct comparisons with systemic azoles underscore the necessity for prospective randomized trials (197).
Posaconazole Prophylaxis for Influenza-Associated Pulmonary Aspergillosis
In critically ill influenza patients, posaconazole meets pharmacokinetic targets for prophylaxis but not treatment because of saturable protein binding (198). In a randomized trial, IAPA incidence was not significantly reduced with posaconazole prophylaxis (5.4% vs. 11.1%; p = 0.32). Crucially, 71% of IAPA cases occurred within 48 hours of ICU admission, with 53% mortality despite treatment; thus, while pharmacokinetic data support prophylactic feasibility, the early onset of most IAPA cases limits prevention (199).
Cost-effectiveness of Posaconazole Prophylaxis
Although posaconazole has a higher acquisition cost compared with some older antifungals like fluconazole or itraconazole, several pharmacoeconomic studies have shown it to be cost-effective. The higher drug cost is often offset by a significant reduction in costs associated with treating breakthrough IFIs, including shorter hospital stays and lower mortality.
Primary antifungal prophylaxis is generally cost-effective, with optimal duration typically ranging from several weeks to 6 months depending on patient risk and clinical context (182). Multiple studies and economic models consistently show that primary antifungal prophylaxis reduces IFIs and is cost-effective, or even cost-saving, compared with no prophylaxis in high-risk hematologic and transplant populations. Among antifungal agents:
- Posaconazole and voriconazole are often the most cost-effective for preventing IFIs, especially in AML and allogeneic HSCT (200).
- Itraconazole (especially oral solution) is also cost-effective, particularly in settings where drug costs are a major concern.
- Mold-active triazoles (posaconazole, voriconazole) are generally preferred over fluconazole for high-risk patients due to better efficacy and favorable cost-effectiveness profiles, despite higher drug acquisition costs (181).
A decision tree model built on the findings from a randomized controlled trial comparing posaconazole with itraconazole/fluconazole showed that posaconazole prophylaxis resulted in a lower incidence of IFDs and associated mortality compared with fluconazole or itraconazole (201). The study also included a cost-effectiveness analysis evaluating the economic benefit of posaconazole as an alternative prophylactic option in this patient population. Posaconazole was associated with improved efficacy and an overall cost reduction of approximately C$4259 per patient (202,203).
Optimal Duration of Prophylaxis
The optimal duration of posaconazole prophylaxis varies according to the underlying condition and the duration of the high-risk period:
- Patients with AML/MDS undergoing chemotherapy: Prophylaxis is typically initiated at the start of chemotherapy and continued until neutrophil recovery.
- Allogeneic HSCT recipients with GVHD: Prophylaxis is extended, often until the patient is no longer receiving high-dose immunosuppressive therapy or as specified by institutional protocols.
- HSCT recipients without GVHD: Prophylaxis is generally administered from the start of conditioning or transplant through day 75 to 100 and may be prolonged in the setting of ongoing immunosuppression or active GVHD (13).
Posaconazole versus Other Antifungal Agents for Prophylaxis
Compared with Fluconazole and Itraconazole
Posaconazole is generally considered superior to fluconazole for prophylaxis in high-risk patients. While fluconazole is effective against Candida species, it lacks significant activity against molds like Aspergillus. Posaconazole’s broad-spectrum activity, including Aspergillus and Mucorales, makes it the preferred agent for patients at high risk for mold infections. It has also shown superior efficacy compared to itraconazole in preventing IFIs (11,181).
Compared with Voriconazole
Both posaconazole and voriconazole are mold-active triazoles. While both are effective for prophylaxis, direct comparison data are limited. Some studies suggest similar efficacy but different safety profiles, with voriconazole often having a higher rate of symptomatic adverse events, while posaconazole may have more liver function test abnormalities (188,204).
Compared with Isavuconazole
Isavuconazole is another broad-spectrum triazole. While a viable option, it is less extensively studied for prophylaxis than posaconazole. Its use is often guided by specific patient factors, such as drug-drug interactions or tolerability. In a large retrospective cohort study using the TriNetX database, antifungal prophylaxis outcomes in 4068 propensity-matched neutropenic adults with AML receiving chemotherapy were compared. Posaconazole was associated with significantly lower 30-day mortality compared to voriconazole or isavuconazole (10.0% vs. 12.0%; hazard ratio (HR) 0.82, p = 0.003) and reduced incidence of shock (14.3% vs. 15.8%; HR 0.89, p = 0.037). However, this survival benefit was accompanied by higher hospitalization rates (57.8% vs. 54.4%; HR 1.15, p < 0.001). No significant differences were observed in respiratory failure or disseminated candidiasis (205). These findings suggest a survival benefit with posaconazole in high-risk patients, balanced against increased healthcare utilization, emphasizing the need for individualized prophylactic strategies.
Compared with Micafungin
In a randomized study comparing micafungin and posaconazole for antifungal prophylaxis in patients with acute leukemia or myelodysplastic syndrome, micafungin showed efficacy comparable to posaconazole in preventing fungal infections during chemotherapy-induced neutropenia (206).
Prophylaxis During Combined Treatment with Hypomethylating Agents and Venetoclax (A BCL-2 Inhibitor)
Patients with AML undergoing remission induction with hypomethylating agents (HMAs) combined with venetoclax are also considered high-risk and require mold-active prophylaxis. In this setting, azole antifungal co-administration necessitates dose adjustment: venetoclax should be reduced by 75% with posaconazole and by 50% with fluconazole (207,208).
Posaconazole in the Treatment of Invasive Fungal Infections
Among all currently available triazoles, posaconazole possesses the broadest spectrum of activity, encompassing not only yeasts like Candida and Cryptococcus but also a wide range of opportunistic and endemic molds. Its unique activity against the Mucorales order distinguishes it from fluconazole and voriconazole, making it a critical option for clinicians (209,210).
Invasive Aspergillosis
In the specific context of invasive aspergillosis, posaconazole has recently been validated as a robust first-line therapy. For decades, voriconazole was the standard of care for primary invasive aspergillosis treatment (15). However, a phase 3, randomized, double-blind, non-inferiority trial including 575 patients established posaconazole as a highly effective and safer alternative. In this global study, the primary endpoint of all-cause mortality up to day 42 was 15% for the posaconazole group and 21% for the voriconazole group, meeting the criteria for non-inferiority (17). Posaconazole was associated with significantly fewer treatment-related adverse events (30% vs. 40%), particularly in terms of visual disturbances (2% vs. 10%) and psychiatric disorders such as hallucinations (2% vs. 8%), which are frequently limiting factors in voriconazole therapy (17). This trial supports the use of posaconazole as an essential primary option, particularly for patients at risk of voriconazole-related toxicities.
Beyond its role in primary treatment, posaconazole remains a cornerstone for salvage therapy in patients who are refractory to or intolerant of conventional antifungal agents like amphotericin B or itraconazole (7). In an externally controlled trial including 107 patients with refractory invasive aspergillosis, posaconazole monotherapy demonstrated an overall success rate of 42%, compared to 26% in a retrospective control group. This therapeutic benefit was consistent across high-risk patient subsets, including those with hematological malignancies and hematopoietic stem cell transplant recipients (7). Subanalyses have confirmed its efficacy in high-risk populations with underlying renal impairment (creatinine clearance <50 mL/min), where overall response rates remained consistent at approximately 49%, indicating that the drug is well tolerated regardless of baseline renal function (16).
Crucially, pharmacokinetic analysis from this trial established a clear exposure-response relationship, where patients achieving a mean average concentration (Cavg) of 1.25 mg/L experienced a 75% response rate, compared to only 24% in those with significantly lower drug exposure (7). These findings underscore the absolute necessity of achieving adequate serum levels to maximize the probability of clinical success in difficult-to-treat infections. International guidelines strongly recommend TDM to ensure trough levels remain above 1.0 mg/L during active treatment (211). However, pharmacokinetic analysis of the phase 3 study that compared posaconazole and voriconazole in the treatment of invasive aspergillosis patients revealed no exposure-response relationship for posaconazole efficacy or safety. For voriconazole, patients in the highest trough concentration quartile had higher day 42 mortality, though no clear safety trends emerged. Neither antifungal demonstrated a strong exposure-response relationship across the studied dose ranges (212).
Duration of Antifungal Treatment
Treatment duration for invasive aspergillosis must be individualized based on clinical improvement, the degree of persistent immunosuppression (especially neutrophil recovery), and radiological response. International guidelines generally recommend a minimum of 6 to 12 weeks of therapy. For patients with hematologic malignancies, therapy should be continued until resolution of all signs and reversal of the underlying deficit in host defenses (15,211,213).
Mucormycosis
The activity of posaconazole against mucormycosis remains one of its most clinically distinguishing features (209). While L-AmB is generally recommended for first-line therapy, posaconazole is frequently employed as salvage treatment or part of an oral step-down regimen (210). Data from the MoveOn study, a matched-pair analysis of patients in the FungiScope registry, evaluated the effectiveness of the newer posaconazole formulations in this setting. Favorable responses were observed in 80% of patients receiving first-line posaconazole and in 50% of those receiving it for salvage therapy (214). By day 42, all-cause mortality was lower in the posaconazole groups compared to standard amphotericin B controls. Despite the small sample sizes inherent to studies of rare infections, the high survival rates associated with posaconazole tablets, and IV formulations suggest they are viable alternatives, particularly in patients with baseline renal impairment who cannot tolerate the nephrotoxicity of polyenes (214). Furthermore, in patients with CF suffering from allergic bronchopulmonary aspergillosis, posaconazole has proven more effective than comparator triazoles at reducing Aspergillus-specific IgE levels, with its efficacy showing a direct inverse correlation with therapeutic drug levels (215).
Rare Fungal Infections
The management of rare hyaline molds and dematiaceous fungi further highlights posaconazole’s broad utility (210,216). For invasive fusariosis, posaconazole has demonstrated a success rate of approximately 48% to 50% in salvage settings (210,216). Similarly, for scedosporiosis caused by the Scedosporium apiospermum complex, posaconazole serves as a valuable alternative to voriconazole due to its low MICs (217). However, its activity against L. prolificans (formerly Scedosporium prolificans) remains poor, as this pathogen is intrinsically resistant to almost all available antifungals (217). For black fungi causing chromoblastomycosis or mycetoma, posaconazole displays potent in vitro activity with MICs typically below 0.5 mg/L, and European guidelines support its use as a primary or salvage option in these rare diseases (216,217). In a systematic literature review, posaconazole treatment demonstrated favorable clinical outcomes in most patients with hyalohyphomycosis (58.5%, 62/106), chromoblastomycosis (90.5%, 19/21), and mycetoma (100%, 5/5) (218).
Invasive Fungal Infections in Critically Ill Patients
Optimizing posaconazole therapy in critically ill patients requires a complex understanding of its pharmacokinetics within the ICU. Critically ill patients, such as those with IAPA or CAPA, often experience altered volumes of distribution and unpredictable drug clearance. Recent population pharmacokinetic modeling of IV posaconazole in ICU patients has shown that the standard dosing regimen (300 mg daily) frequently fails to achieve the treatment target trough of 1.0 mg/L. To mitigate this risk, weight-based loading regimens have been proposed: 300 mg every 12 hours for patients <100 kg and 300 mg every 8 hours for those ≥100 kg for the first 2 days of treatment. Furthermore, increasing the maintenance dose to 400 mg daily has been predicted to achieve a probability of target attainment exceeding 90%. Achieving these targets rapidly is essential given the 50% mortality rate associated with viral-fungal co-infections in the ICU (219,220).
Therapeutic drug monitoring is recommended in patients with oral bioavailability problems, particularly when using the oral suspension or treating refractory infections (209,211). For prophylaxis, a trough level of >0.7 mg/L is generally targeted, while for active treatment, levels of >1.0 mg/L to 1.25 mg/L are recommended (7,209,211). Some experts advocate for even higher targets, up to 1.8 mg/L, to ensure efficacy against pathogens with higher MICs (45,209). While the newer tablet and IV formulations achieve these targets more consistently, subtherapeutic levels still occur in 10–28% of patients, often due to factors like diarrhea, hypoalbuminemia, or severe mucositis (209,220). Because posaconazole accumulates intracellularly (reaching concentrations in pulmonary alveolar cells that are 30 to 60 times higher than in plasma), serum levels may occasionally underestimate the drug’s activity at the site of infection. Nevertheless, plasma TDM remains the only validated method for ensuring adequate exposure in clinical practice (209,210).
Breakthrough Infections During Posaconazole Prophylaxis
The epidemiology of breakthrough IFIs (bIFIs) under posaconazole pressure is a growing concern that reflects shifts in the fungal landscape (221). Real-world data from the CAESAR 2.0 study in China, involving over 2000 patients, revealed that even with the widespread use of mold-active prophylaxis (voriconazole 44% and posaconazole 32%), the cumulative incidence of IFD remained 6.3%. Pathogens identified in these breakthrough cases included a significant proportion of Mucorales (13%) and Candida species (18%), particularly non-albicans Candida strains with reduced azole susceptibility (222). Similarly, a large Spanish multicenter study found that prior antifungal therapy widely determines the epidemiology of bIFIs, with invasive aspergillosis being the most frequent breakthrough after posaconazole prophylaxis (221). The rise of azole-resistant A. fumigatus, driven by mutations like TR34/L98H, further complicates therapy (211). This evolution necessitates aggressive diagnostic approaches, including tissue biopsies and molecular identification, to guide appropriate therapy once breakthrough occurs. A prospective observational study was conducted across 19 hemato-oncology centers in Germany between September 2011 and December 2013, enrolling 2440 patients with AML and 627 with acute lymphoblastic leukemia (ALL). A total of 179 cases of invasive aspergillosis were identified, comprising six proven and 173 probable cases. Among these patients, two had received itraconazole prophylaxis, six had received voriconazole prophylaxis, and 53 had received posaconazole prophylaxis. Of the 77 A. fumigatus isolates obtained from patients, only two exhibited azole resistance. One of the patients was under posaconazole prophylaxis, and the other patient was receiving voriconazole prophylaxis (223). However, according to a recent literature review, 54.7% of the 75 fungal isolates (the minority tested for antifungal susceptibility) from patients with bIFIs during posaconazole prophylaxis were resistant to posaconazole (30). These findings underscore the dynamic nature of bIFIs, necessitating a careful evaluation that accounts for variations in epidemiological settings. A recent multicenter case-control study identified that most bIFIs were attributed to presumably posaconazole-susceptible pathogens with no clear association with posaconazole underexposure (224).
At a single center in Cologne, a prospective registry over nine years documented bIFI in patients receiving posaconazole prophylaxis. Among 250 patients undergoing AML induction chemotherapy, 51 developed IFIs, while 43 IFIs occurred among 409 patients who had undergone allogeneic HSCT. In a subset of these patients, management strategies diverged: some were switched to a different antifungal class (primarily L-AmB), whereas others continued posaconazole with interventions aimed at increasing its serum bioavailability. A comparison of continuing prophylaxis versus switching antifungal class as first-line treatment revealed no significant difference in either treatment response or survival (225). In a multicenter study from Italy, among 127 patients initiated antifungal therapy due to posaconazole failure, the type of antifungal agent had no impact on 30-day mortality (226). A Turkish multicenter study of 230 acute leukemia or allo-HSCT recipients reported that among patients on posaconazole prophylaxis who developed bIFI, switching to voriconazole was successful in 6/9 patients, while L-AmB achieved response in 3/6 patients (171). Current guidelines most consistently recommend initiating treatment with a different class of antifungal agent than was used for prophylaxis, particularly in patients without a suspicion of underexposure. A switch to L-AmB is frequently recommended as first-line empirical therapy, particularly for suspected mucormycosis or severe disease. Then, the choice of salvage therapy should be guided by the specific pathogen (227).
Prior use of posaconazole also significantly impacts the performance of non-culture-based diagnostic biomarkers. The sensitivity of the galactomannan (GM) assay in both serum and bronchoalveolar lavage (BAL) fluid is known to decrease in patients receiving mold-active prophylaxis or treatment (211,228). In a study of hematology patients, posaconazole prophylaxis resulted in a non-significant decrease in GM sensitivity and a simultaneous increase in specificity, suggesting that GM alone may not be sufficient to rule out infection in these populations. Repeated measurements of serum GM in patients on posaconazole do not always show the linear progression typical of untreated infections (218). Given the reduced diagnostic utility of serum biomarkers, bronchoscopy should be prioritized for patients with suspected bIFI who are receiving mold-active prophylaxis. The diagnostic accuracy of GM testing in BAL specimens was not significantly impacted by posaconazole prophylaxis or short-term (3 days) antifungal therapy. Consequently, clinicians should maintain a low threshold for utilizing different GM cut-off values or incorporating other tools such as polymerase chain reaction (PCR) or computed tomography (CT)-guided biopsies when clinical suspicion of infection remains high despite mold-active treatment (218,228).
Candida Infections
Posaconazole displays a broad in vitro activity spectrum against both C. albicans and non-albicans Candida species. It is currently approved for the prophylaxis of Candida infections in high-risk immunocompromised patients and for the treatment of oropharyngeal candidiasis, including cases refractory to fluconazole or itraconazole. However, posaconazole is not currently recommended as a first-line agent for invasive candidiasis or candidemia due to the lack of large-scale clinical trials in this specific therapeutic area (15). Epidemiological data from the CAESAR 2.0 study in China show that Candida species were identified in 18% of bIFIs in allo-HSCT recipients despite mold-active prophylaxis. Among these cases, Candida tropicalis was the most frequent pathogen (14.6%), reflecting a shift toward non-albicans Candida species under triazole pressure. While posaconazole retains activity against C. krusei, it shows high cross-resistance with fluconazole in Candida glabrata isolates. In managing breakthrough candidemia, current guidelines suggest a switch to different drug classes, such as echinocandins or amphotericin B, depending on local susceptibility patterns (215,222).
Posaconazole in Special Populations
Allogeneic Stem Cell Transplant Recipients
Patients with hematologic malignancies and those who have undergone allogeneic HSCT are at the highest risk for IFIs. In these patients, the incidence of IFIs ranges from 7% to 15%. The pre-engraftment and post-engraftment periods are associated with different risk factors for IFIs (3). In patients who develop IFIs after allogeneic HSCT, the 1-year mortality rate has been reported to range between 36% and 72% (229).
The most common causative agent of IFIs in these patients is Aspergillus spp. The incidence of invasive aspergillosis is 8%, and in 93% of cases it is associated with pulmonary involvement (3). The most frequently identified risk factors for invasive aspergillosis or invasive mold infections include extensive or severe chronic GVHD, viral respiratory tract infection, high-dose corticosteroid therapy, acute GVHD (≥ grade II), and HLA mismatch (229).
According to the ECIL guideline recommendations for prophylaxis, posaconazole (tablet or oral suspension) is recommended at a B-II level during the pre-engraftment period (in patients at low or high risk for invasive mold infections), whereas fluconazole is recommended only for low-risk patients at an A-I level. In the post-engraftment period, posaconazole is recommended with an A-I level of evidence (13).
In a study comparing posaconazole and voriconazole for the primary treatment of invasive aspergillosis, the 42-day mortality rates in allogeneic HSCT patients were 22% (14/65) in the posaconazole group and 15% (9/59) in the voriconazole group, and posaconazole was found to be non-inferior to voriconazole (17).
Patients Receiving Targeted Therapy (Checkpoint Inhibitors, Kinase Inhibitors, and BCL-2 Inhibitors)
In a study of 102 lung cancer patients treated with checkpoint inhibitors, 44 (43.1%) developed pulmonary infections. Among these infections, C. albicans was reported as the causative agent in five cases and Aspergillus spp. in four cases (230).
Among 147,854 patients receiving checkpoint inhibitor therapy in whom immune-related adverse events were reported, 18,068 infectious adverse events were documented. Among the infectious adverse events with an identified causative agent, fungal pathogens accounted for 4.57%. Pneumocystis jirovecii was the most frequently identified fungal pathogen, followed by Candida spp. and Aspergillus spp. (231).
In patients with CLL and non-Hodgkin lymphoma (NHL) treated with BTK inhibitors such as ibrutinib, the risk of infection with Aspergillus spp. has been reported to be higher than the standard risk described for patients with CLL and NHL. It is recommended that these patients be evaluated for the need for antifungal prophylaxis or screening for fungal infections. Drug-drug interactions between ibrutinib and azoles limit the use of azoles in primary prophylaxis (232,233).
Among 350 patients treated with anti-apoptotic BCL-2 inhibitors such as venetoclax, which are used in the treatment of CLL, only two cases of IPA were identified (234). Because venetoclax is metabolized via the CYP3A4 enzyme, it has clinically relevant interactions with azole antifungal agents (235).
Recipients of Chimeric Antigen Receptor T-Cell Therapy or Bispecific Monoclonal Antibodies
In patients receiving CAR T-cell therapy, the IFIs have been reported to range between 2% and 5% (236,237). In studies including patients who received fluconazole or echinocandin prophylaxis during the neutropenic period, low rates of invasive yeast infections were reported. These low rates support the use of early prophylaxis against yeasts. Regarding mold prophylaxis, posaconazole prophylaxis is recommended for high-risk patients, such as those with a history of prior fungal infection or those who develop severe CAR T-cell-related complications (235,238).
In patients receiving bispecific monoclonal antibody therapy, the risk of developing IFIs is quite low (239). Antifungal prophylaxis other than for P. jirovecii pneumonia (PJP) is not recommended unless the patient has a history of prior fungal infection, prolonged neutropenia, or has received high-dose corticosteroid therapy for more than 2 weeks. For invasive candidiasis or aspergillosis, it is recommended that standard treatment guidelines be followed (240).
Similarly, the risk of IFIs has been found to be low with monoclonal antibody therapies targeting lymphoid or myeloid cell surface antigens (CD19, CD20, CD52, CD22, CD30, CD33, and CD38) (232,241).
Pediatrics and Geriatrics
Posaconazole has been reported to be used as primary antifungal prophylaxis in children. It has also been used for secondary prophylaxis, as salvage therapy for aspergillosis and mucormycosis, and as step-down therapy in mucormycosis (242–244).
Because delayed-release tablets reach target concentrations faster, their use is recommended in children who can swallow tablets. The oral suspension, tablet, and IV formulations of posaconazole are not bioequivalent, so formulation-specific recommendations should be considered when switching between them (245).
One of the most common adverse effects of the IV formulation in children is hepatotoxicity. It is recommended that treatment may be restarted once liver enzyme levels return to normal (246).
Recommendations for geriatric patients and pharmacokinetic parameters do not differ from those in adult patients. However, caution should be exercised with respect to drug-drug interactions (247).
Organ Dysfunction (Hepatic and Renal)
During posaconazole therapy, transient elevations in serum aminotransferase levels occur in approximately 2–12% of patients. These increases are usually mild, asymptomatic, and self-limiting, and only rarely lead to discontinuation of treatment (248). Symptomatic adverse effects occur at higher doses. Therefore, TDM is important not only for efficacy but also for safety (88). Severe hepatotoxicity is very rare (≤1%). Most studies have found no association between the duration of posaconazole exposure and hepatotoxicity (9). Concomitant use of posaconazole with other hepatotoxic medications should be avoided (172).
In a study evaluating 144 patients who received posaconazole in the form of oral tablets or suspension, the rate of renal dysfunction was 11.8% (249). Two cases of acute kidney injury developing during posaconazole therapy have also been reported (250).
Gaps in Clinical Practice Related to Invasive Pulmonary Aspergillosis Diagnosis, Prophylaxis, and Treatment
Invasive pulmonary aspergillosis remains a difficult disease to manage in clinical practice, with several grey areas and challenges in diagnosis, prophylaxis, and treatment in both neutropenic and non-neutropenic patients.
Diagnostic Challenges
The greatest challenge lies in the timely and accurate diagnosis of IPA. Delays are associated with increased mortality and usually compromise the treatment of the underlying condition.
Clinical and Radiological Presentation
Symptoms like fever, cough, and dyspnea occur in most respiratory infections in immunocompromised hosts. Fever could be related to several infectious and non-infectious causes, whereas the characteristic pleuritic chest pain in a febrile neutropenic patient suggestive of IPA is infrequent.
Classic radiological signs like the “halo” (early) or “air-crescent” (late) signs on CT are highly suggestive but not always present. The halo sign may also be seen in other conditions (251). In addition, their appearance can be transient, and they are less common in non-neutropenic patients.
Limitations of Conventional Gold-Standard Diagnostic Methods in Clinical Practice
While pathological examination is regarded as the definitive diagnostic standard, obtaining a lung biopsy is often impractical because of severe thrombocytopenia or the clinical condition of the patient. Fungal cultures can take days to grow and are often negative even in active disease. Furthermore, a positive culture from a non-sterile site (such as sputum or deep tracheal aspirate) may indicate colonization (252).
Challenges with Non-Culture-Based Tests
The performance of the serum GM assay varies significantly by patient population. It has excellent utility in patients with hematological malignancy but much lower sensitivity in non-neutropenic patients (253). Successive serum sampling and testing are usually required because a single sample may be negative. While monitoring of the high-risk neutropenic patient with serum GM testing at least twice weekly is beneficial for early diagnosis of IPA, turnaround times exceeding 24 hours lead to delay in diagnosis. The sensitivity of serum GM assay is much lower in patients on mold-active prophylaxis (33). False positives can occur with certain antibiotics or other fungal infections (254–256).
Galactomannan testing of BAL fluid is more sensitive but requires an invasive bronchoscopy (257,258). Aspergillus PCR in serum, plasma, and BAL fluid is a useful test to prompt early treatment, and it has been included in some IPA guidelines or consensus reports (23,259). A modified method for detecting GM using a Microcon filter significantly increased sensitivity without adversely affecting specificity. Nevertheless, the associated cost increase posed a major limitation (260,261).
A rapid, bedside test, such as a lateral flow assay (LFA) for IPA, would be ideal for early diagnosis. Studies are promising for LFA for GM (262–265), but they are not widely used in clinical practice, so their impact on patient management remains unclear.
Non-Neutropenic Patient
Invasive pulmonary aspergillosis has been mostly studied in the neutropenic patient with hematological malignancies, yet risk factors do exist in non-neutropenic patients such as corticosteroid therapy, cirrhosis, chronic obstructive lung disease, post-influenza or post-COVID-19 infection. Until recently, diagnosis of IPA in these patients lacked a standard approach, but several consensus reports defining IPA have been published to aid clinicians in the ICU, IAPA, and CAPA (23,266,267).
Challenges in Prophylaxis
Prophylaxis aims to prevent IPA in high-risk patients, but its implementation is not straightforward in clinical practice.
Patient Population Heterogeneity and Risk Stratification
The risk for IPA is not uniform. It is highest in patients with prolonged, profound neutropenia and lung transplant recipients. New biological agents are introduced to treat certain malignancies or autoimmune diseases, and data on IPA risk with newer agents are insufficient to determine which patients need prophylaxis. On the other hand, a patient’s risk changes over time. Therefore, it is better to be flexible rather than stick to a fixed-duration prophylaxis. Anti-mold prophylaxis is much less clear in the non-neutropenic patient population with an increased risk of IPA.
Pharmacological and Drug-Related Challenges
Azoles with anti-mold activity are potent inhibitors of the cytochrome P450 system. They have significant interactions with chemotherapy agents, immunosuppressants (tacrolimus, sirolimus), and many other drugs, complicating dosing and increasing toxicity. Adverse effects of these azoles, such as hepatotoxicity, QTc prolongation (voriconazole), and visual disturbances (voriconazole), may or may not be directly related to serum levels. In addition, bioavailability of azoles can be a serious issue, especially with mucositis, diarrhea, and genetic polymorphisms. Therapeutic drug monitoring of voriconazole is recommended because of its variable bioavailability and drug-drug interactions (268,269); however, it is not performed in many centers. Delayed-release posaconazole tablets have overcome the poor and variable absorption of the oral suspension and eliminated the need for routine TDM except in patients with oral bioavailability problems, potential major drug interactions or suspected treatment failure (269).
Other Challenges
Breakthrough Infections: Diagnosis of a bIFI under mold-effective prophylaxis may be problematic. This could be related to insufficient prophylaxis (low serum levels) or emergence of a resistant fungus (270,271). Increased isolation of Aspergillus fumigatus strains with TR34/L98H and TR46/Y121F/T289A mutations has been suggested to result from excessive azole use in agriculture, but the impact of mold-active prophylaxis remains unclear. Some centers have reported an increase in the incidence of mucormycosis cases with the use of voriconazole (272,273).
Strategic Challenges
Implementation of prophylaxis vs. empirical vs. diagnostic-driven (pre-emptive) treatment strategies is one of the major dilemmas clinicians face. Each strategy has its pros and cons. While the guidelines and literature data help the clinician choose one strategy, the local incidence and resistance patterns, as well as available resources, are of utmost importance. Widespread and unnecessary use of anti-mold prophylaxis driven by limited diagnostic means at a particular center may lead to emergence of resistant fungal pathogens and less choice of systemic antifungals to treat a breakthrough IFD.
Therapeutic Challenges
Even after diagnosis, optimal treatment is fraught with challenges. Problems related to drug toxicity and tolerability complicate not only prophylaxis but treatment as well.
One question that may arise during treatment is what the optimal strategy would be when a patient fails first-line therapy. Failure may be due to drug resistance, unfavorable drug pharmacokinetics and pharmacodynamics, or host factors. A switch to another antifungal class is usually recommended but lacks data to promote this strategy strongly (274). The evidence for combination antifungal therapy (e.g., voriconazole + an echinocandin) is also weak. On the other hand, immune reconstitution may lead to an increased inflammatory response that could be mistaken for failure of antifungal therapy.
Duration of antifungal therapy in IPA should be decided based on each patient’s characteristics, including clinical response, evolution of radiological findings during treatment, status of the underlying condition, and potential for continued immunosuppressive therapy.
When Should Posaconazole Be Avoided?
Posaconazole is an effective broad-spectrum antifungal agent with several advantages, including fewer drug interactions than voriconazole, availability of both IV and oral formulations, and a need for TDM only with poor oral bioavailability. However, certain host factors may preclude its use.
Hypersensitivity
Posaconazole should not be used in patients with a known history of hypersensitivity to posaconazole itself or to other azoles because of the possibility of cross-reaction.
Serious Drug Interactions
Posaconazole is a potent inhibitor of the CYP3A4 enzyme pathway and a substrate of P-gp. Therefore, its use must be avoided if the patient is on treatment with a CYP3A4 substrate such as quinidine because of the risk of QTc prolongation that may lead to fatal arrhythmias such as TdP, and statins highly dependent on CYP3A4 such as simvastatin and lovastatin due to high risk of rhabdomyolysis (275,276).
Prolonged QTc Interval
Posaconazole itself can cause QT prolongation. It should be avoided in patients with QT prolongation or those with conditions that predispose to arrhythmias (e.g., cardiomyopathy, bradycardia, hypokalemia, hypomagnesemia) (277).
Severe Hepatic Impairment
Although dose adjustment is not required for hepatic impairment, its use in patients with severe hepatic impairment (Child-Pugh Class C) has not been adequately studied. Therefore, it should be used in these patients only if the benefit outweighs the risk, with close monitoring for toxicity. In an analysis of the manufacturer’s global safety database, 516 cases involving 618 hepatobiliary adverse events in posaconazole-treated patients were evaluated. The most frequently reported events included hyperbilirubinemia, hepatic failure, and hepatotoxicity. Notably, 69% of cases involved concomitant use of medications with known hepatotoxic potential, with 45% receiving drugs associated with severe or mild-to-moderate drug-induced liver injury. These findings suggest that concurrent hepatotoxic medications significantly contribute to the development of hepatic adverse events in patients receiving posaconazole, underscoring the need for careful medication review and monitoring (172).
Renal Impairment
The IV formulation is solubilized with a cyclodextrin derivative, SBECD, which accumulates in patients with moderate to severe renal impairment (creatinine clearance <50 mL/min) and may cause nephrotoxicity. Oral formulation is preferred in these patients (278).
Pregnancy and Lactation
The FDA assigned no pregnancy category, but it was harmful in animals; thus, it should be avoided in pregnancy unless the potential benefit justifies the potential risk to the fetus. It is unknown whether posaconazole is excreted in human milk. Because of the potential for serious adverse reactions in breastfeeding, a decision should be made to either discontinue nursing or discontinue the drug (279).
The Therapeutic Role of Posaconazole in Breakthrough Infections
Breakthrough IFD may develop during antifungal prophylaxis and treatment, especially in severely immunosuppressed patients with prolonged neutropenia. Posaconazole has been approved as salvage treatment in invasive aspergillosis, fusariosis, chromoblastomycosis and mycetoma, and coccidioidomycosis in Europe (76).
Invasive Aspergillosis
Studies of posaconazole salvage treatment have shown a success rate around 40% (7,16,280). Walsh et al. (7) compared 107 patients intolerant of or refractory to conventional antifungal therapy who received posaconazole oral suspension with 86 external control subjects. The overall success rate was 42% for posaconazole recipients and 26% for control subjects (odds ratio [OR]: 4.06; 95% CI: 1.50–11.04; p = 0.006). In another study, 53 patients who received posaconazole salvage therapy were compared to 52 contemporary control patients who received high-dose lipid formulation of amphotericin B (HD-LPD/AMB; ≥7.5 mg/kg per day) and 38 other control patients who received caspofungin plus HD-LPD/AMB. The overall response rate to salvage therapy was 40% for posaconazole, 8% for HD-LPD/AMB (p ≤ 0.001), and 11% for combination therapy (p < 0.002) (280). Of note, posaconazole used in these salvage studies was all oral suspension.
Fusariosis
The clinical form of fusarium infection depends on the portal of entry and the immune status of the host. In immunocompromised patients, the most frequent clinical form of invasive fusariosis is that of disseminated disease with pneumonia, multiple skin lesions, and positive blood cultures with a very high mortality rate in persistent neutropenia (281,282). In a retrospective analysis of 21 patients with proven or probable invasive fusariosis who were refractory to or intolerant of standard antifungal therapy, oral posaconazole suspension (800 mg per day in divided doses) was used as salvage therapy from three open-label clinical trials (283). Ten patients (48%) responded to posaconazole; for patients who recovered from myelosuppression, the success rate was 67%, compared with 20% for those with persistent neutropenia. Posaconazole is recommended as salvage treatment in the ECMM guideline (284).
Chromoblastomycosis and Mycetoma
Chromoblastomycosis is a chronic subcutaneous infection caused by dematiaceous fungi—most commonly Cladophialophora carrionii, Fonsecaea compacta, Fonsecaea pedrosoi, and Phialophora verrucosa (285). The infection is difficult to cure, and relapses are common. A high response rate (90.5%, 19 of 21 patients) was reported by Bernauer et al. (218) in their systematic literature review.
Mycetomas are localized infections that involve cutaneous and subcutaneous tissue, fascia, and bone (285). Lesions consist of abscesses, granulomata, and draining sinuses from which granules may be recovered. Mycetoma is difficult to cure, and therapy includes amputation of the affected limb or large surgical excision of the affected tissue to reduce the disease burden. Excision alone is rarely sufficient for a complete cure. Clinical data on posaconazole are limited; all five patients with mycetoma were reported to be cured (218).
Coccidioidomycosis
Coccidioidomycosis is a systemic fungal infection caused by C. immitis and Coccidioides posadasii, which are endemic to the Southwestern United States and parts of Mexico, Central, and South America (286). While oral fluconazole is widely recommended as first-line therapy, treatment failure is not uncommon. Posaconazole has proven useful in patients intolerant of, or refractory to, other antifungal agents.
The Current Data About the Off-Label Use of Posaconazole
Mucormycosis
Data suggest posaconazole (especially tablets or IV formulation) is effective in salvage therapy with clinical improvement in ~40–60% of cases. In a systematic review, positive clinical outcomes were observed in 74.8% (1197/1601) of patients treated with posaconazole; 77.1% (894/1159) used posaconazole as first-line therapy and 72.2% (197/273) used it as second-line therapy. Posaconazole has been recommended as primary (2,287) and salvage (2,274,287) treatment of mucormycosis.
Other Infections
Posaconazole has been used successfully in histoplasmosis (288), ocular infections either in its original suspension form (289,290) or as micellar form to increase ocular penetration (291), and refractory superficial fungal infections and onychomycosis (292,293).
Summary of Expert Panel Statements and Recommendations
The recommendations of the expert panel on specific topics are summarized in Tables 4–9.
Conclusion
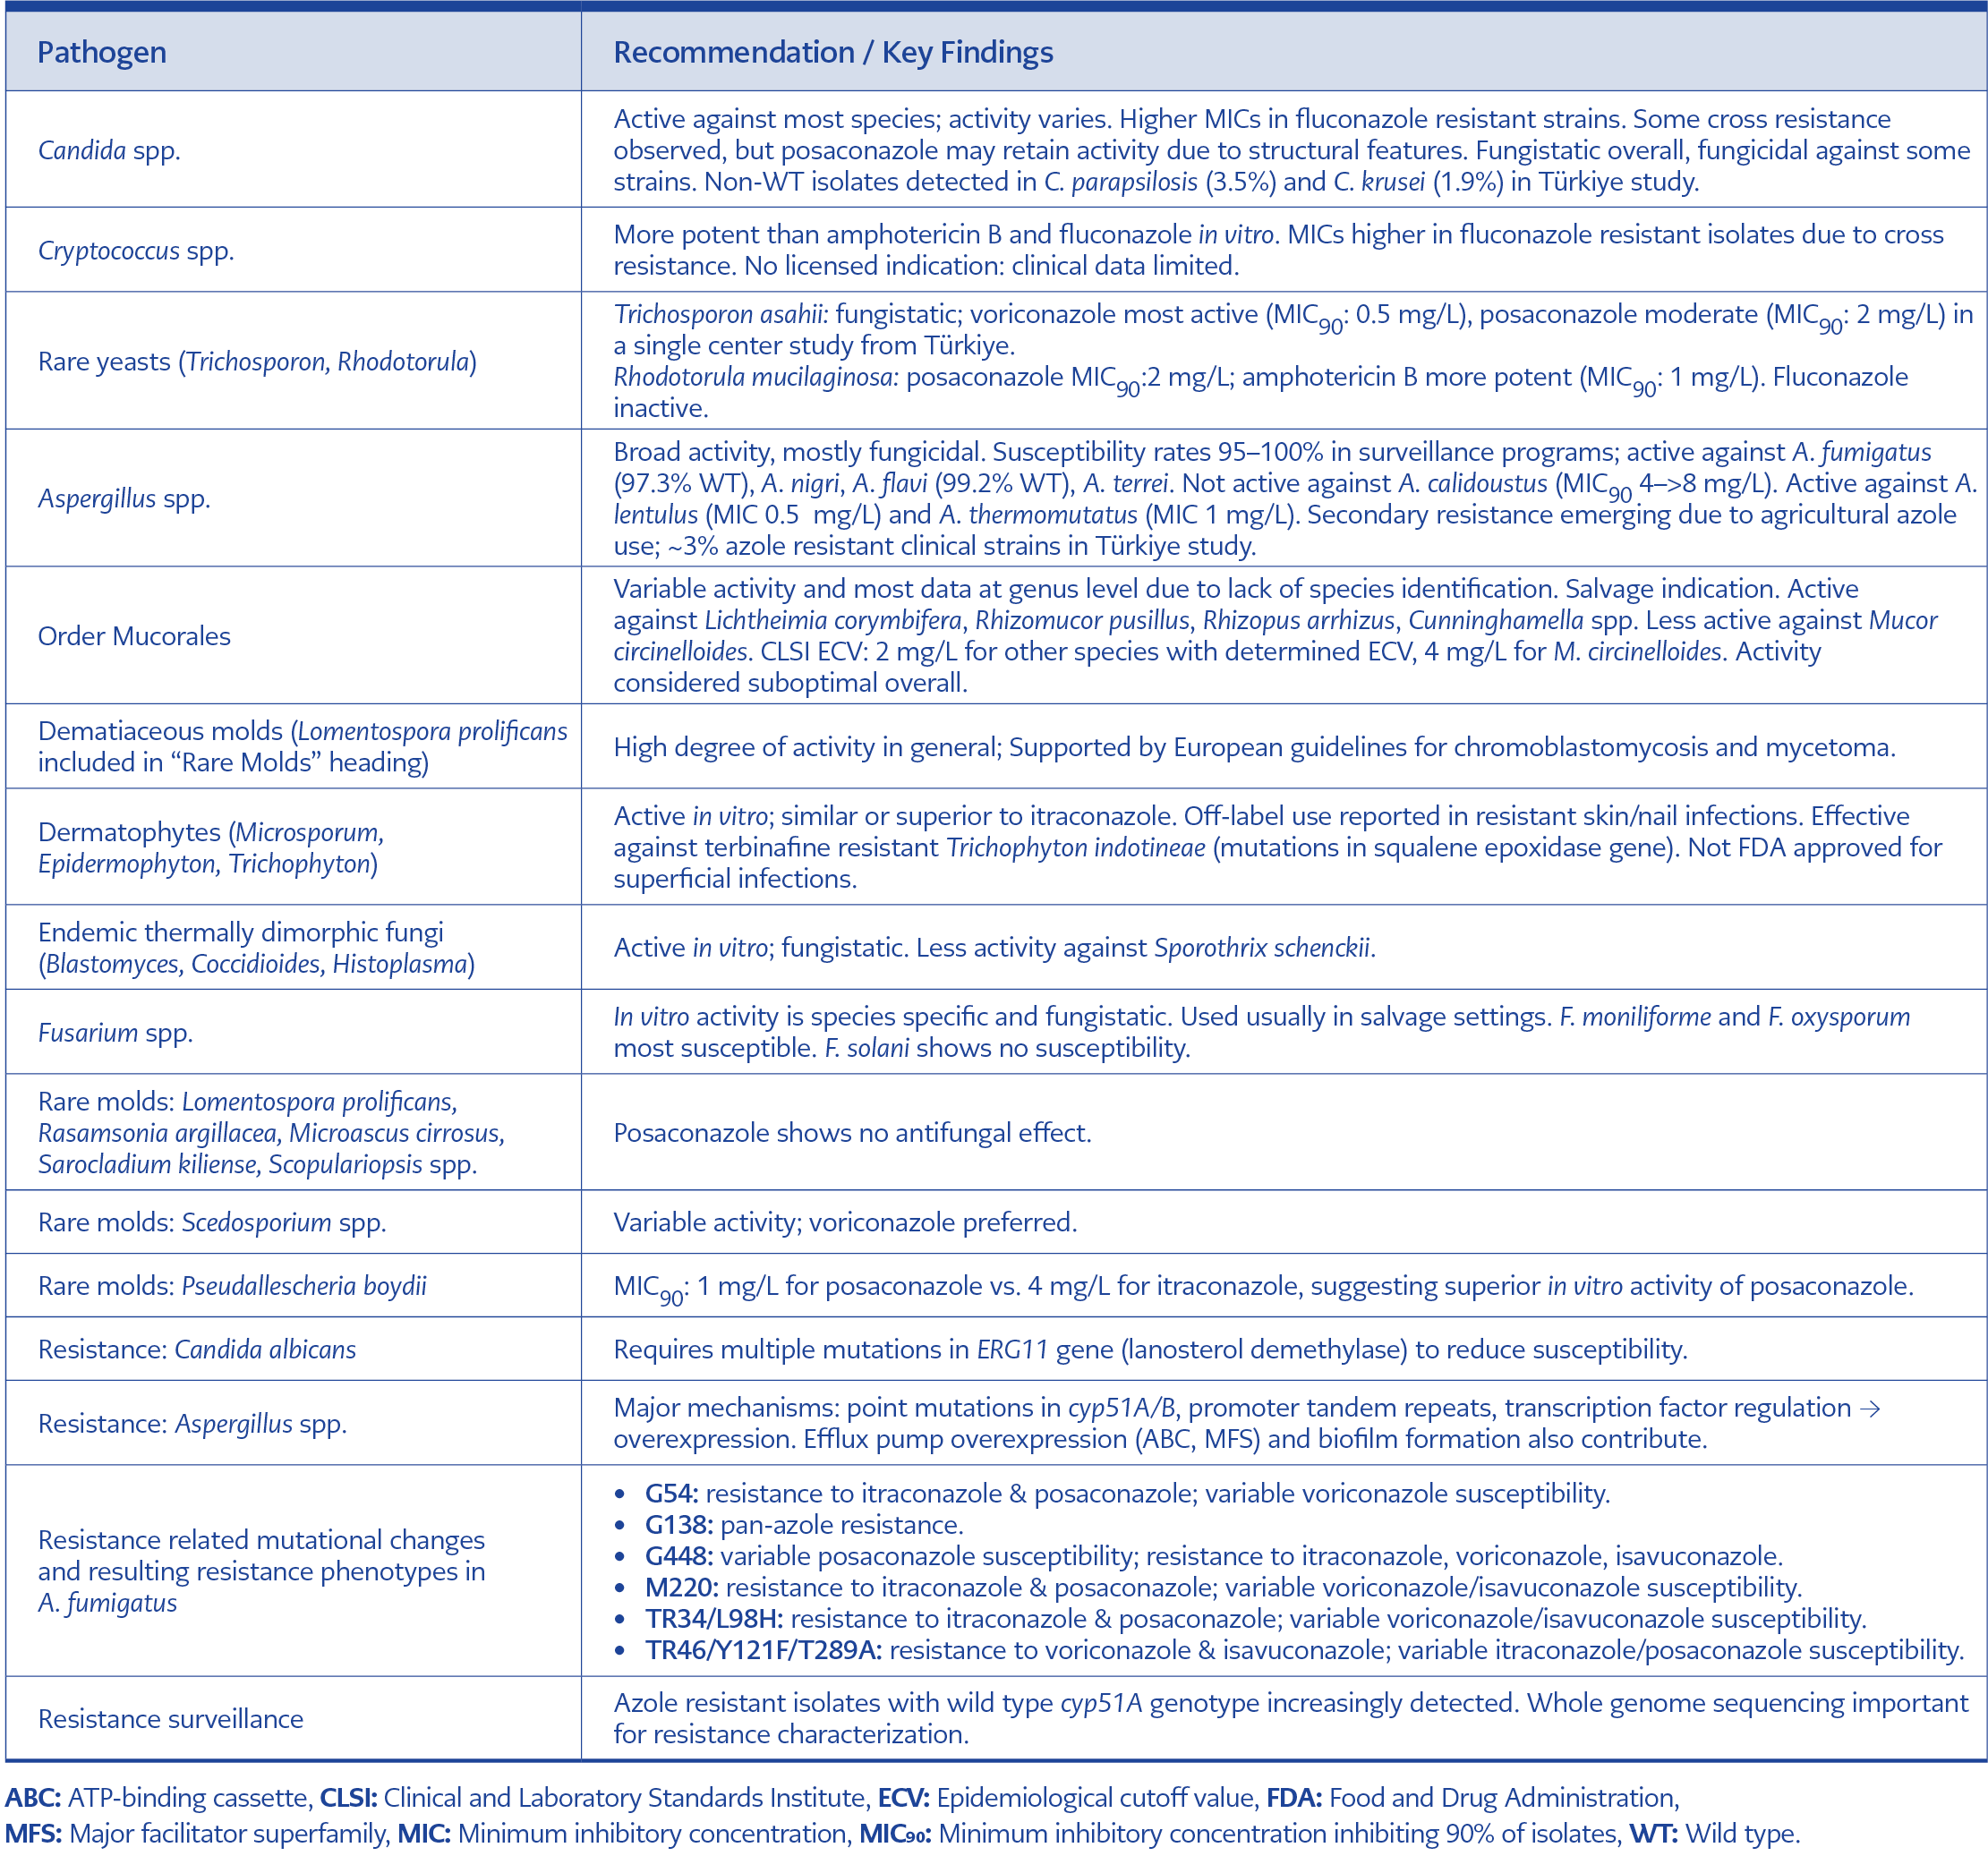
Table 4. In vitro activity and resistance mechanisms of Posaconazole.
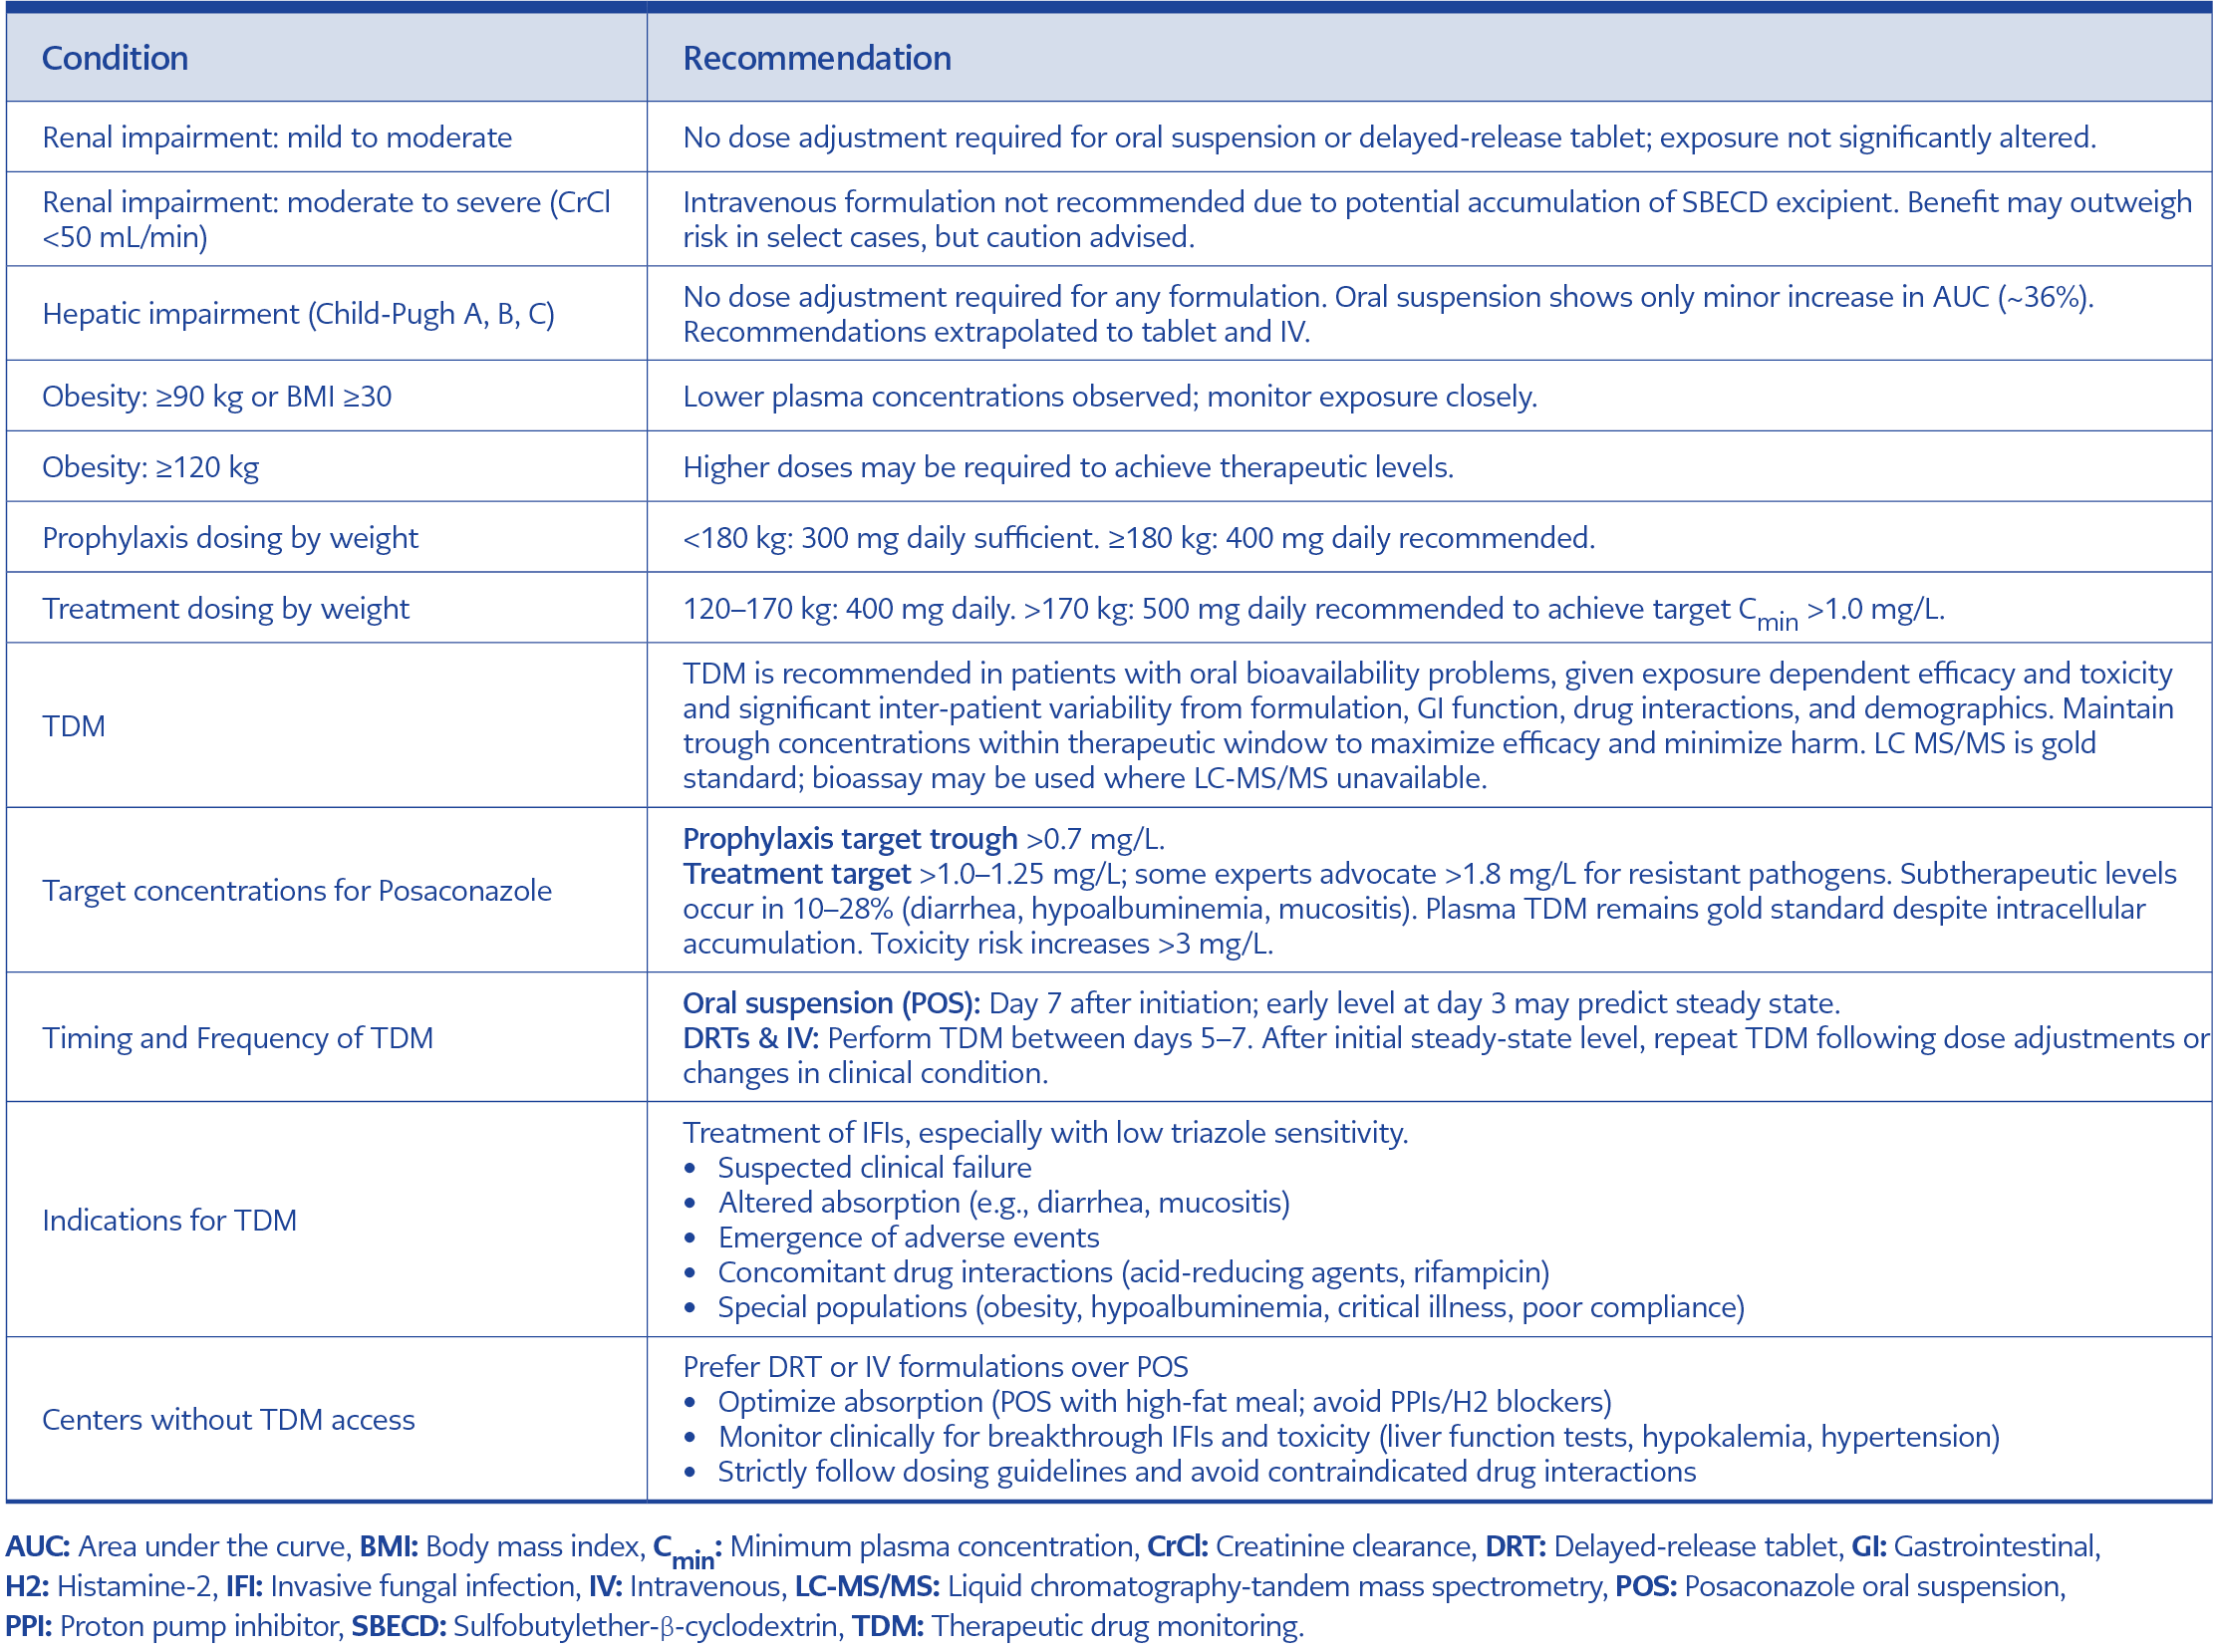
Table 5. Dosing, special clinical conditions and therapeutic drug monitoring.
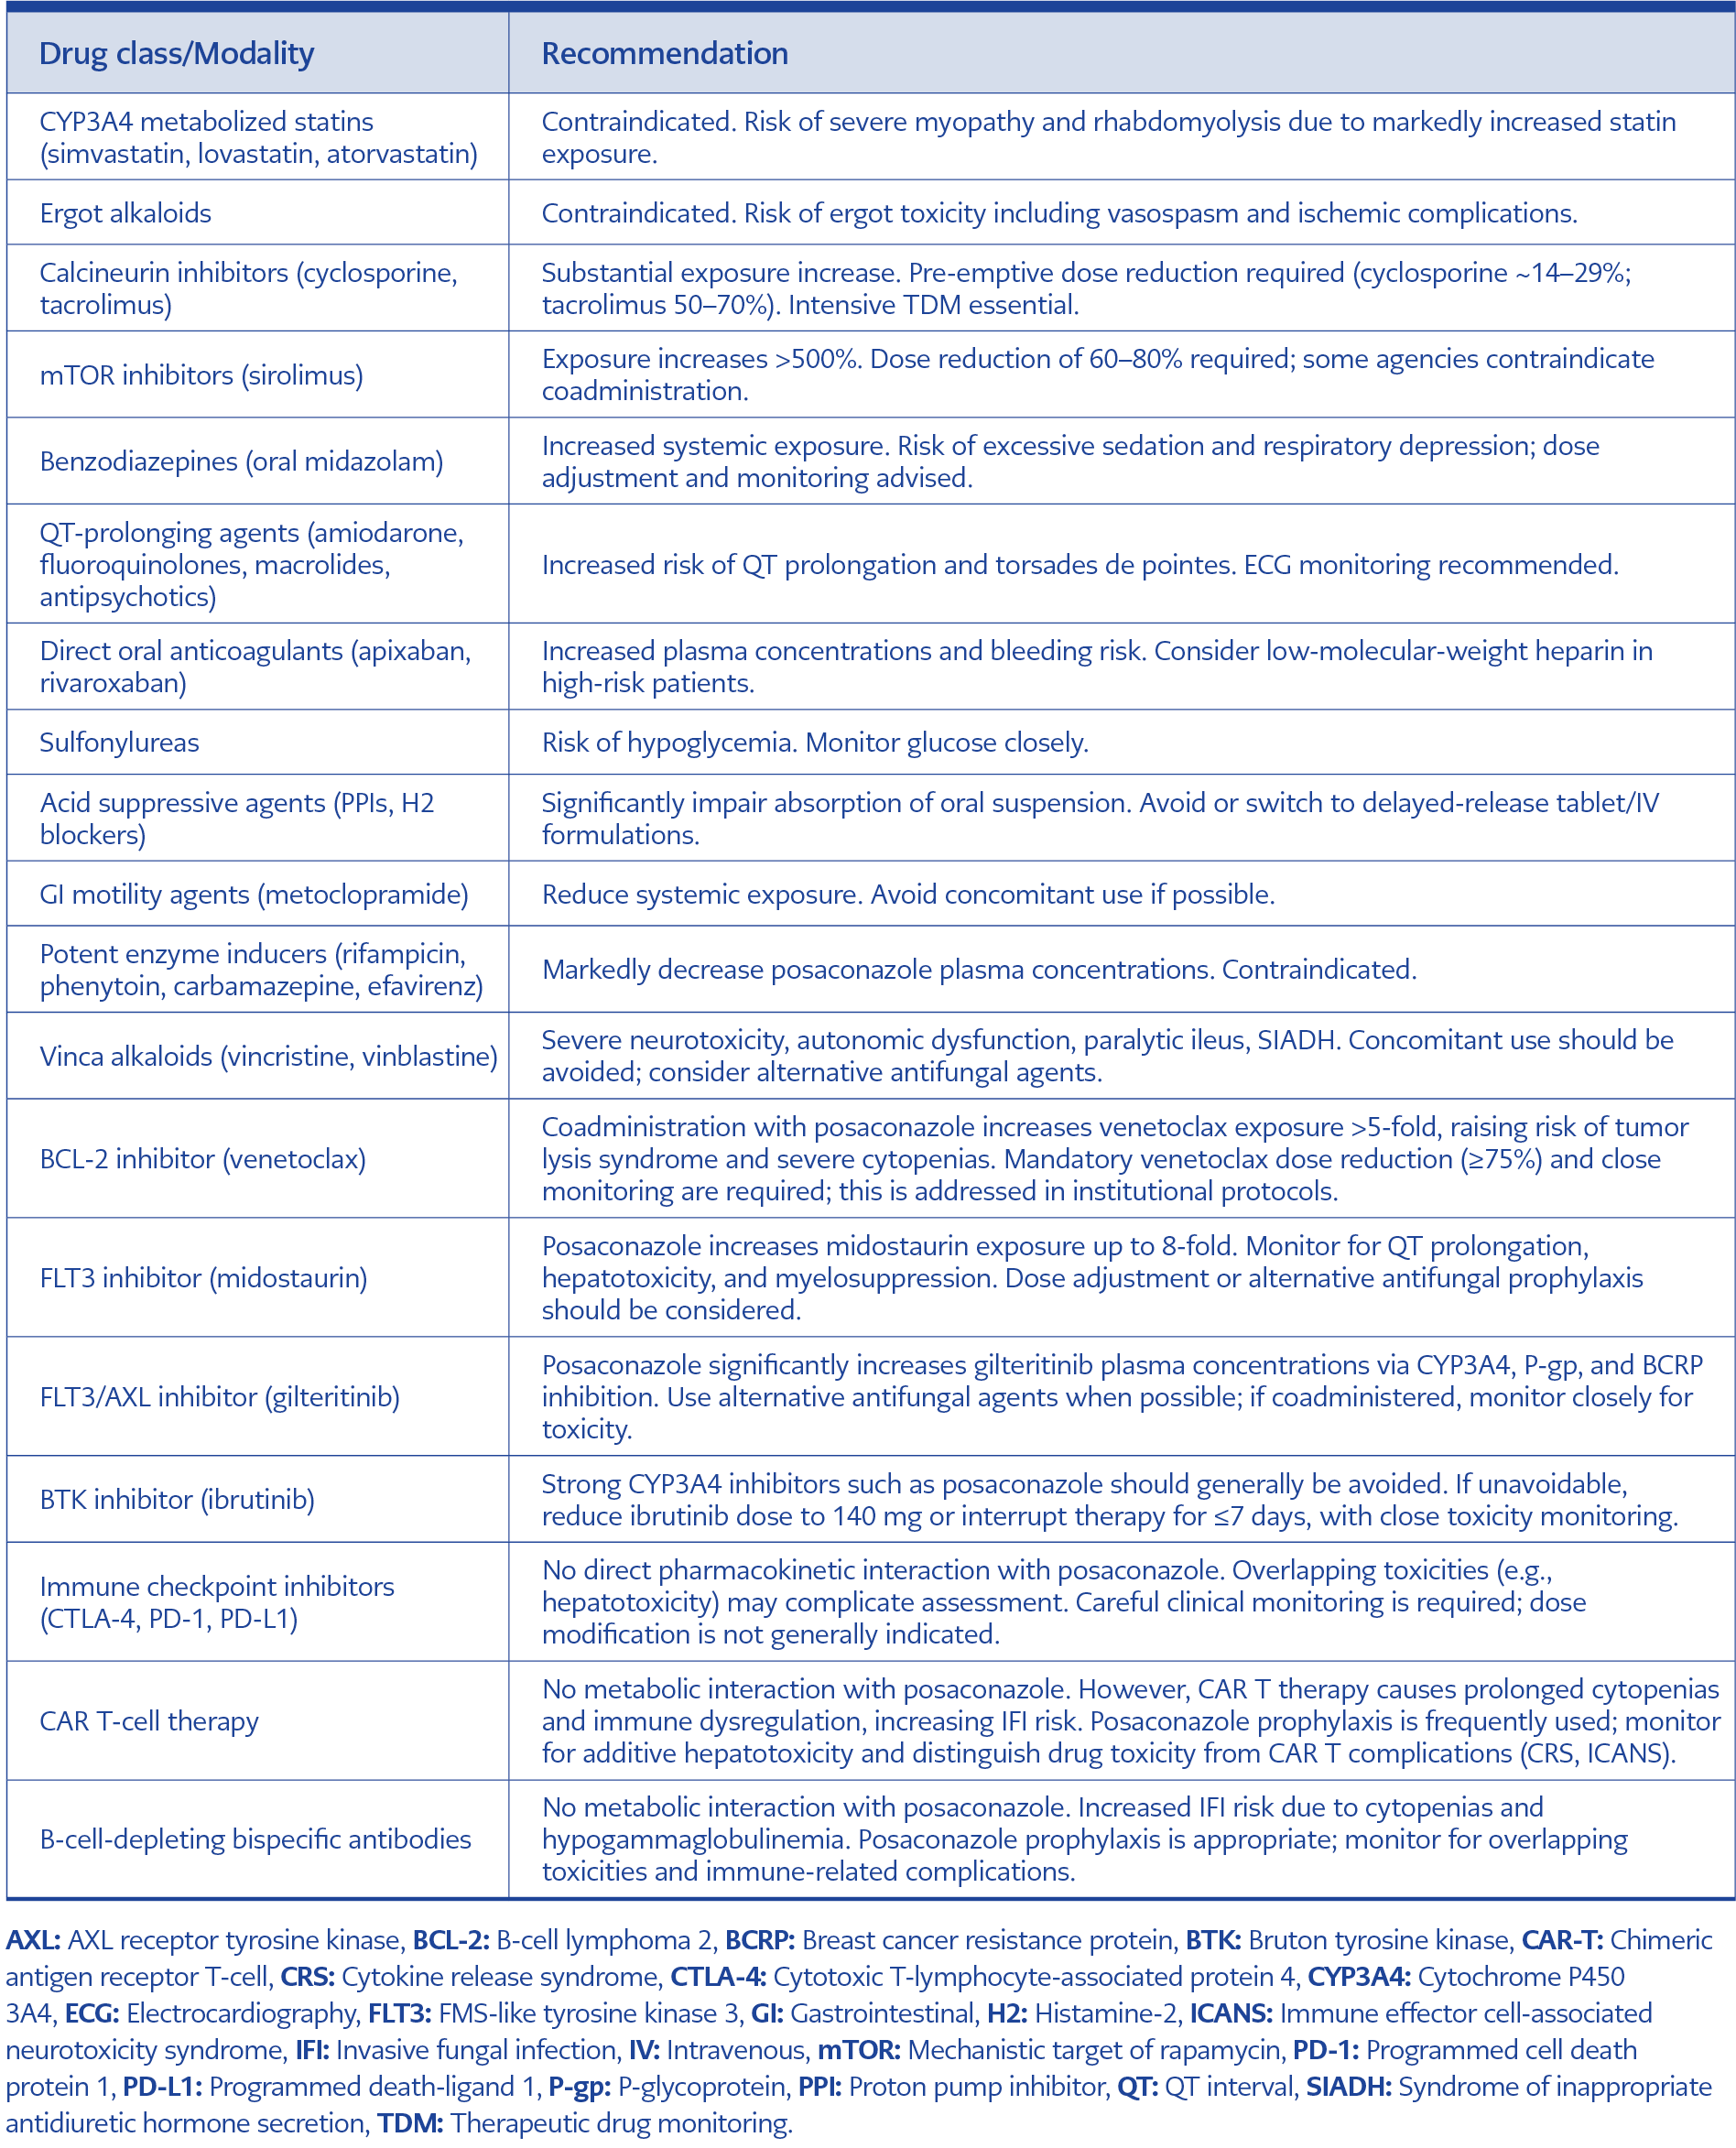
Table 6. Drug-drug interactions.
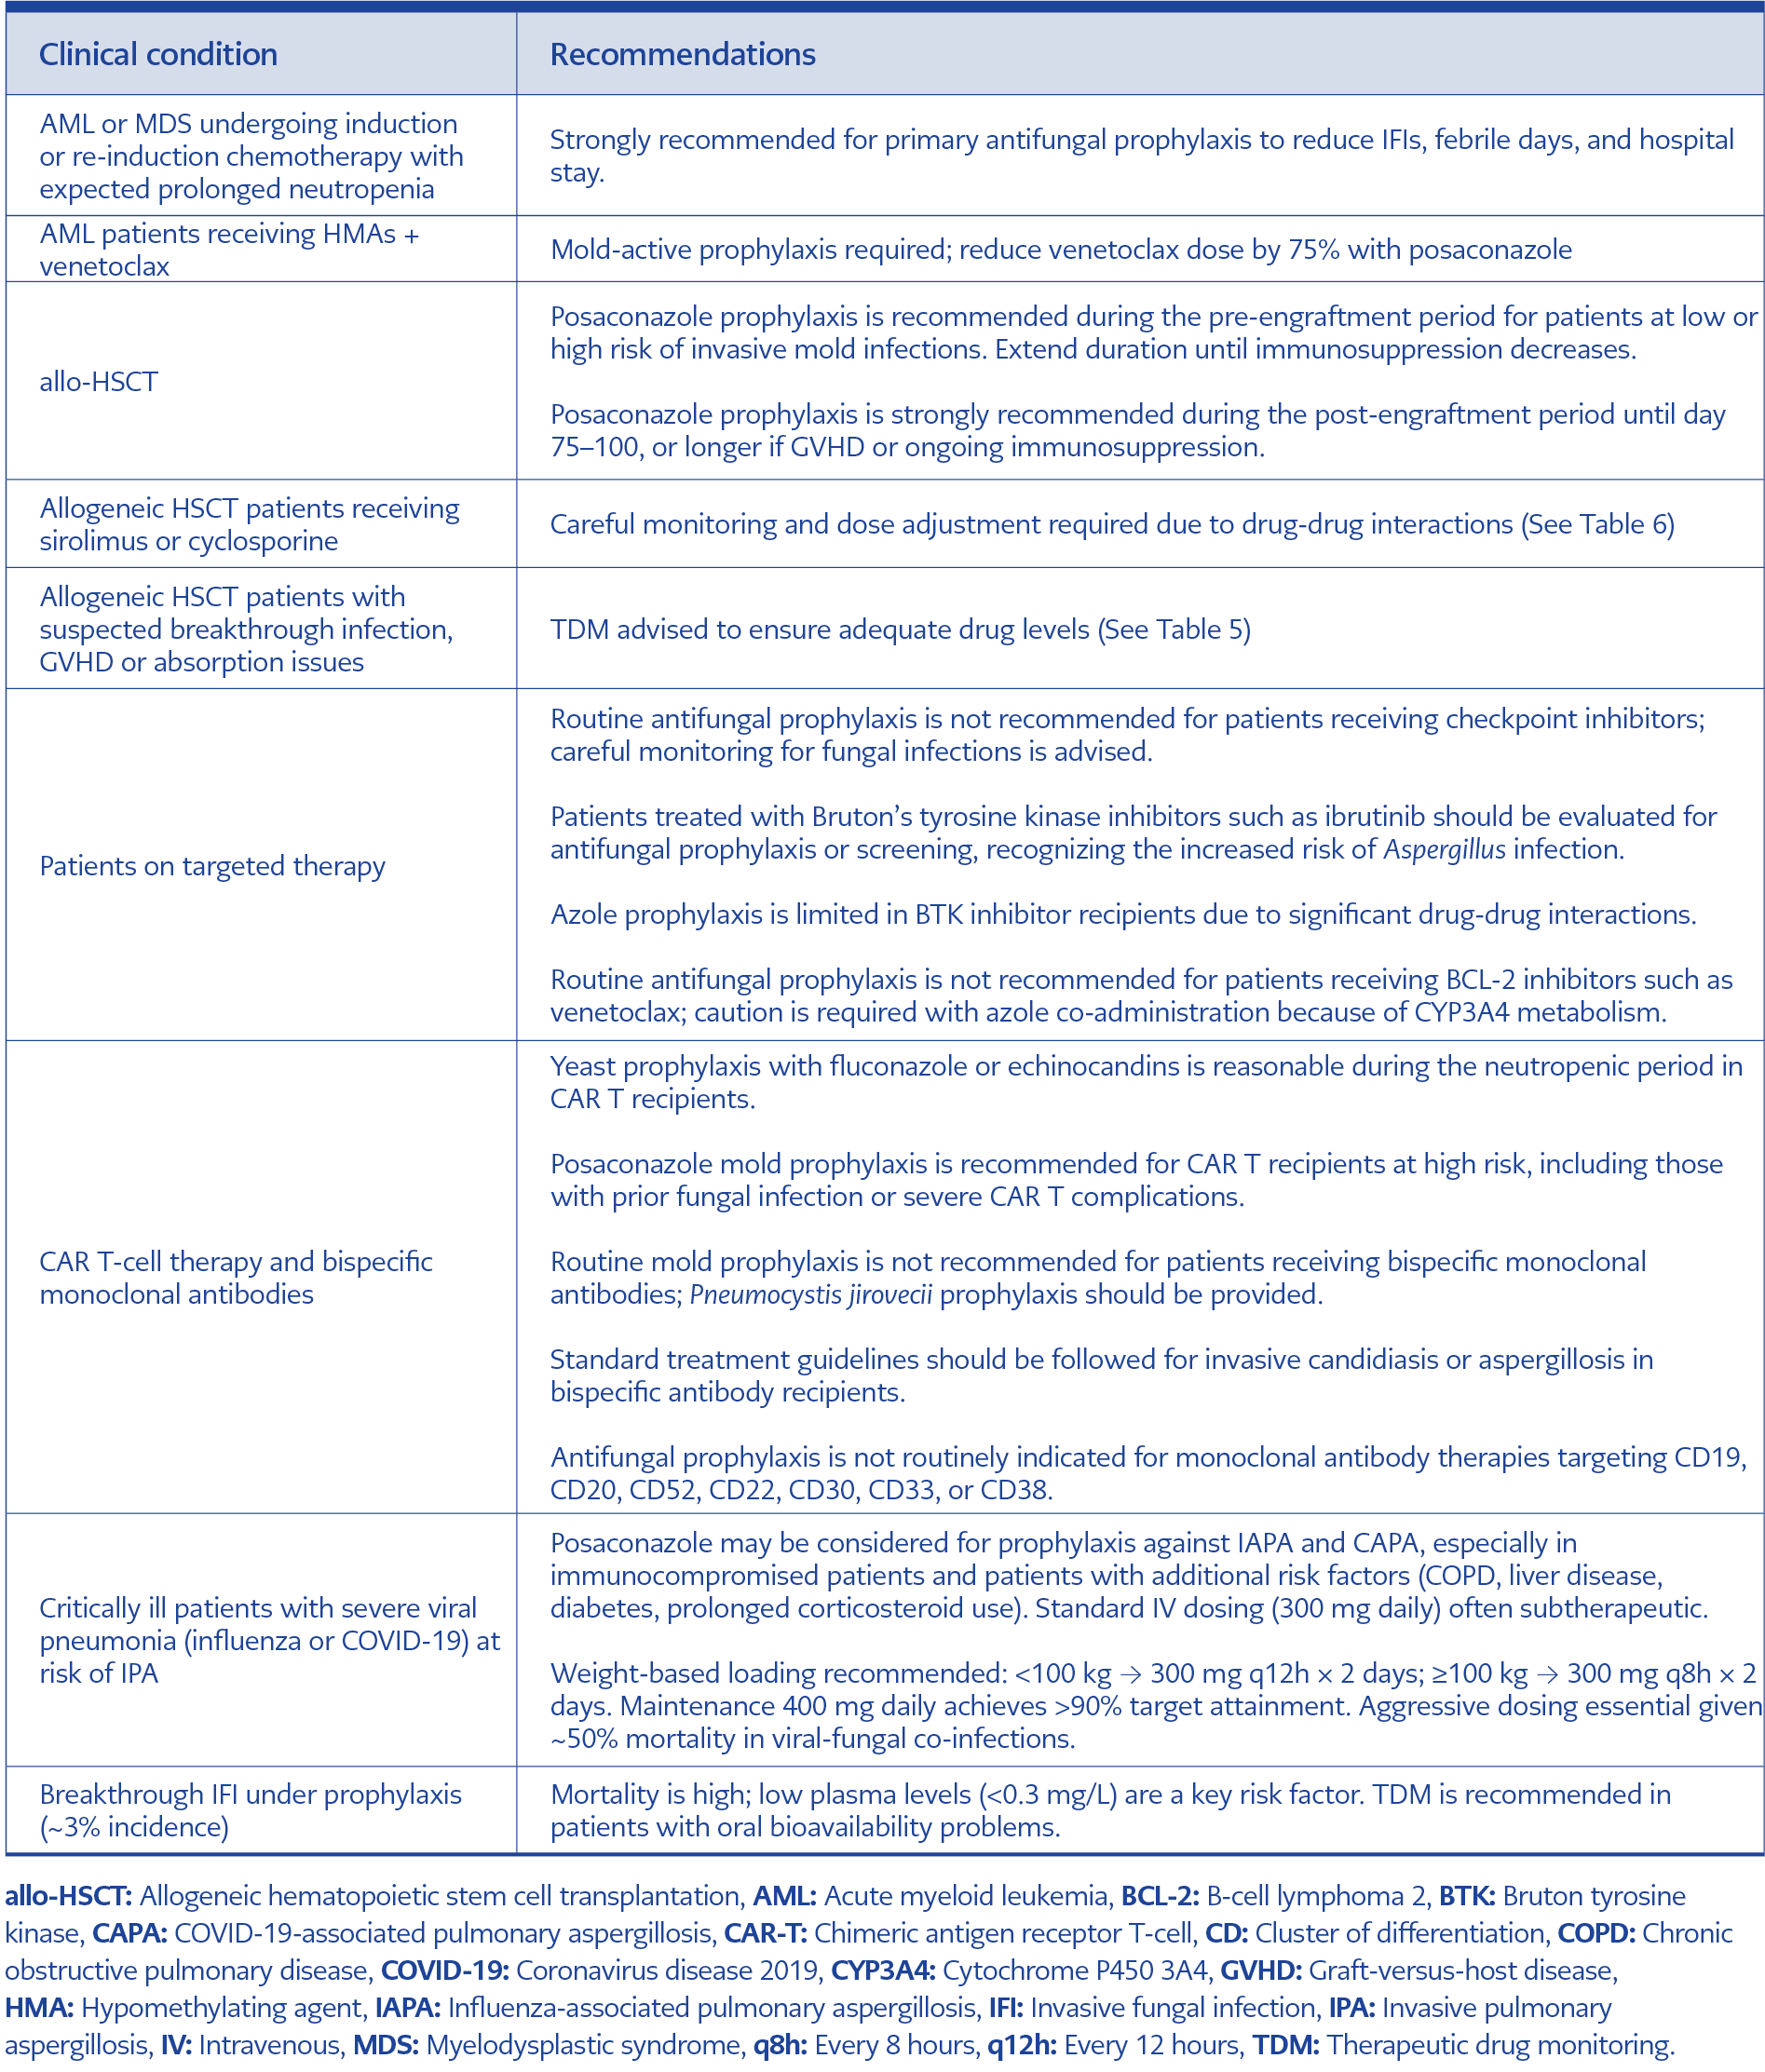
Table 7. Posaconazole prophylaxis.
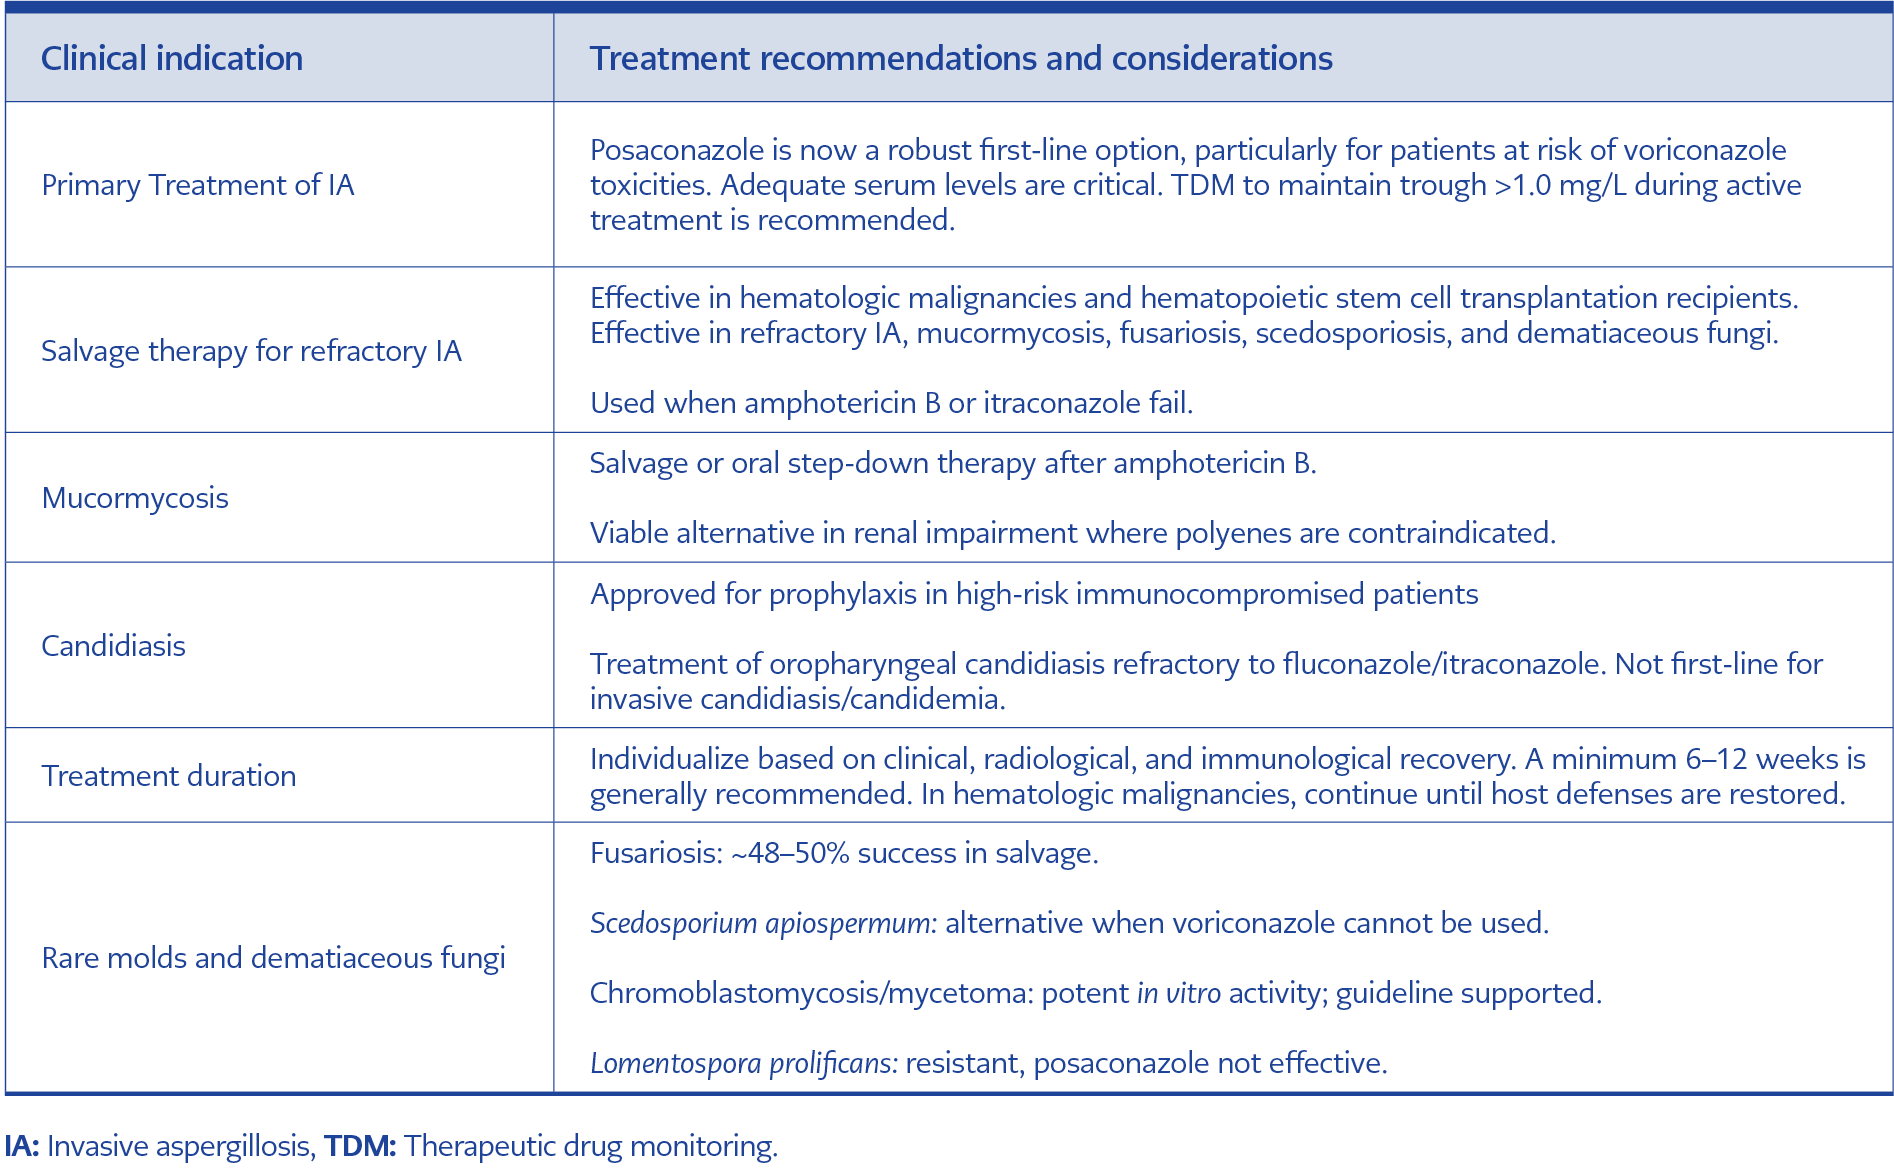
Table 8. Posaconazole treatment.
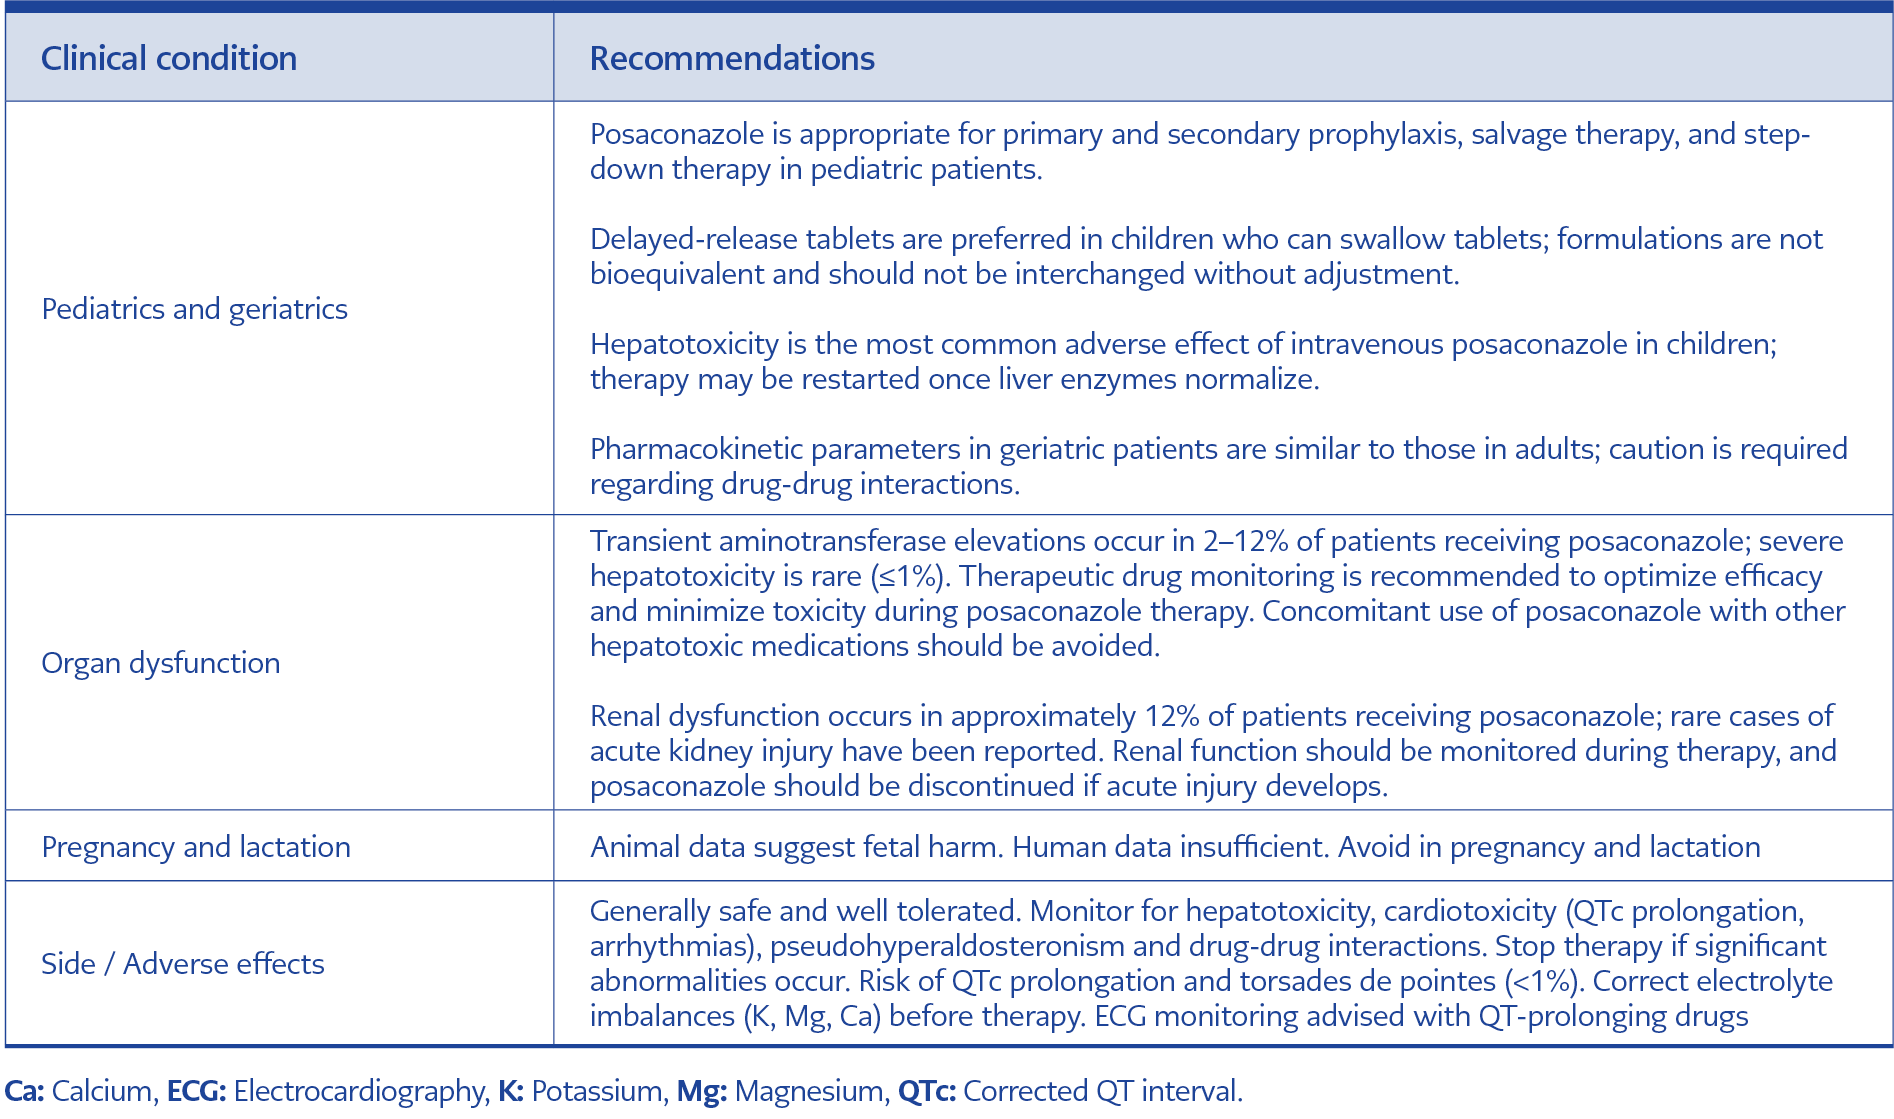
Table 9. Special issues.
Posaconazole has become a cornerstone in antifungal pharmacotherapy, distinguished by its broad-spectrum activity, favorable tolerability, and versatile formulations (294). Its potent efficacy against Aspergillus and Candida species, as well as clinically relevant activity against Mucorales, underscores its unique value in both prophylaxis and treatment of IFIs (2,17,209,214). The introduction of delayed-release tablets and IV formulations has addressed earlier limitations of the oral suspension, ensured more consistent bioavailability, and simplified administration across diverse patient populations. Moreover, its relatively low incidence of hepatotoxicity and manageable drug-drug interaction profile render posaconazole particularly suitable for immunocompromised patients with complex therapeutic regimens, such as those with hematologic malignancies or undergoing allogeneic stem cell transplantation.
Over the past decade, the role of posaconazole has evolved from salvage therapy to a preferred agent in prophylaxis. Randomized controlled trials have demonstrated its superiority over fluconazole and itraconazole in preventing IFIs among patients with prolonged neutropenia or GVHD, leading to significant reductions in IFI-related morbidity and mortality. These findings have been reinforced by meta-analyses and real-world data, which consistently highlight its prophylactic efficacy and safety. In treatment contexts, posaconazole remains an important option for refractory or intolerant cases, with documented success in salvage therapy for IA and mucormycosis. Its inclusion in international guidelines reflects growing consensus on its dual role in prophylaxis and targeted therapy.
Looking ahead, several future perspectives are noteworthy. Therapeutic drug monitoring is recommended to optimize exposure in patients with oral bioavailability problems and in critically ill patients with altered pharmacokinetics. Research into combination antifungal strategies may expand its utility in resistant or mixed infections, addressing the rising challenge of antifungal resistance. Furthermore, real-world evidence from pediatric, geriatric, and critically ill populations will refine its risk-benefit profile and inform individualized dosing strategies. Advances in pharmacogenomics and formulation science also hold promise for enhancing drug delivery, accessibility, and patient-specific tailoring.
In summary, posaconazole represents a paradigm shift in antifungal management, combining potent activity with practical usability. Its strengths in prophylaxis and salvage therapy have already reshaped clinical practice, and its future trajectory points toward precision medicine, novel therapeutic combinations, and expanded applicability across diverse patient populations. Sustained collaboration between clinicians, researchers, and policymakers will be critical to fully realize the potential of posaconazole in safeguarding vulnerable patients against invasive fungal diseases.